• How to Disinfect After Stomach Virus

    A parent kneels on the bathroom tile at 2 a.m., holding paper towels in one hand while a child retches nearby. The obvious mess is easy to see. The less obvious contamination is harder: the flush handle, faucet, light switch, door knob, towels, toothbrush holder, and any object touched while someone was vomiting.

    A stomach-virus cleanup isn't the same as wiping up an ordinary spill. Norovirus can spread through vomit and diarrhea, remain on hard surfaces for days, and resist many everyday cleaning products. The safest approach is a measured process built around physical removal, an appropriate disinfectant, sufficient wet contact time, and cleaning the tools used during the job.

    This guide focuses on how to disinfect after stomach virus exposure, including the steps most household guides skip. The current CDC norovirus prevention guidance recommends a chlorine bleach solution at 1,000 to 5,000 ppm, or an EPA-registered product effective against norovirus. The bleach must remain on the surface for at least 5 minutes before the area is cleaned again with soap and hot water.

    The First Five Minutes After a Stomach Virus Hits Your Home

    The first instinct is usually to grab whatever is closest, perhaps dish soap, a general disinfecting wipe, or a bottle of alcohol-based cleaner. Those products may remove visible grime, but they shouldn't be your only response to a vomiting incident involving suspected norovirus.

    Norovirus is a small, non-enveloped virus, and many ordinary disinfectants don't reliably inactivate it. The contaminated area may also be larger than the visible stain. Vomiting can spread particles onto nearby hard surfaces and objects, especially in a bathroom or cramped bedroom.

    Start by keeping other people and pets away from the area. Open a window if practical, avoid touching your face, and gather disposable towels, gloves, a trash bag, and a disinfectant that specifically states it works against norovirus. Don't begin scrubbing while someone is still actively vomiting unless you need to prevent immediate contact with the material.

    Practical rule: Treat the visible mess as the center of a wider contamination zone. Clean the objects people touched during the incident, not only the tile or floor.

    The CDC's measurable standard is important here. Use a bleach solution in the 1,000 to 5,000 ppm range, keep it wet for at least 5 minutes, then clean the surface again with soap and hot water. That contact time is part of the disinfection process, not an optional waiting period.

    An infographic detailing how norovirus spreads, its longevity on surfaces, and its high contagion level.

    The next few minutes matter, but the next several hours matter more. A proper cleanup takes time because it involves removing organic material, disinfecting surrounding surfaces, laundering fabrics, and dealing with the mop, cloths, bucket, and clothing used during the response.

    Gathering Your Cleanup Kit and Choosing the Right Disinfectant

    Set up the full kit before entering the contaminated area. Repeated trips between a bathroom or bedroom and clean storage areas can spread contamination to your gloves, clothing, hands, and nearby surfaces.

    Gather disposable nitrile gloves, paper towels, sealable trash bags, and a face covering if splashing or airborne droplets are possible. Wear clothing that can go directly into the wash. Keep separate mop heads and microfiber cloths for this job. Two buckets labeled clean and dirty reduce the chance of dipping a used cloth into fresh disinfectant.

    For hard, nonporous surfaces, the CDC recommends a chlorine bleach solution between 1,000 and 5,000 ppm, or an EPA-registered disinfectant effective against norovirus. The EPA's List G database identifies products registered for that pathogen claim. A List G product is not automatically a stronger cleaner. Check its label, EPA registration details, approved surfaces, dilution instructions, and required wet contact time.

    Common shopping-list examples include Clorox Hydrogen Peroxide Disinfecting Wipes, Lysol Brand Bleach Mold and Mildew Remover, and Purell Professional Surface Disinfectant. Formulations and registrations can change, so verify the current label instead of relying on the brand name alone. For surfaces that may be damaged by bleach, use a product whose label specifically permits that surface and states effectiveness against norovirus. Do not improvise with an unverified cleaner.

    Bleach Dilution Chart for Norovirus Cleanup

    Concentration Use case Bleach per gallon Bleach per quart Contact time
    1,000 ppm General hard, nonporous surfaces 5 tablespoons household bleach (6-8.25%) per gallon 1¼ tablespoons household bleach (6-8.25%) per quart At least 5 minutes
    5,000 ppm Heavy contamination and visibly soiled areas 25 tablespoons household bleach (6-8.25%) per gallon 6¼ tablespoons household bleach (6-8.25%) per quart At least 5 minutes

    Use 5 tablespoons per gallon for routine hard-surface disinfection and 25 tablespoons per gallon only for heavy, visibly soiled contamination. Both solutions require at least 5 minutes of wet contact time. Confirm your product's label strength before measuring, since household bleach concentrations vary. The bleach-solution guidance for disinfecting provides further dilution instructions.

    Never mix bleach with ammonia, acids, toilet-bowl cleaner, or another disinfectant. Prepare the solution fresh when possible. A freshly prepared solution should be used within 24 hours, because chlorine can evaporate and weaken it. If storage is necessary, the CDC says to use a stronger stored solution and replace it within 30 days. The CDC technical guidance on chlorine solutions explains this storage distinction.

    Step-by-Step Cleanup From Vomit to Final Rinse

    The order matters. Remove visible material first, clean with detergent and water second, and disinfect third. Applying bleach directly over vomit or stool wastes disinfectant on organic material and makes it harder to achieve reliable surface contact.

    Start with air and protective equipment

    Ventilate the room before you work. Open windows where safe and use an exhaust fan that vents outdoors. Turn off recirculating airflow if it would move contaminated air into other rooms.

    Put on gloves and a face covering. Use paper towels or other disposable absorbent material to collect vomit or stool. Place everything directly into a plastic bag, close the bag securely, and keep it away from clean supplies.

    Clean outward from the visible mess

    Wash the visibly soiled area with detergent and water. Use disposable material for this first pass, and change gloves if they become visibly contaminated. Don't use the same cloth on the floor, toilet, faucet, and door handle.

    Apply the stronger bleach solution, or a labeled EPA-registered norovirus disinfectant, to the contaminated hard surface and the surrounding area that may have received splashes or droplets. Keep the surface visibly wet for at least 5 minutes, following the product label if it requires a longer period.

    The common reversal is the failure point. Bleach can't do its job well when grime and organic matter are still covering the surface.

    Once the primary area is treated, disinfect nearby high-touch points. Include the toilet seat, flush handle, sink faucet, light switch, door knob, cabinet pull, and any shared device or object handled during the incident. Work from cleaner areas toward the bathroom and toilet fixtures so you don't carry contamination back into clean spaces.

    Mop the floor last. Begin at the farthest clean point and work toward the exit. Keep the mop head from returning to a cleaned section, and don't carry an uncovered bucket through other rooms.

    The Sweet Home Cleaning Service guide is useful for identifying overlooked household touchpoints beyond the obvious spill.

    Seal used paper towels, gloves, and disposable materials in an outdoor rubbish container. Reusable cloths and mop heads need their own disinfection process, covered below. Remove gloves without touching the contaminated exterior, then wash your hands thoroughly with soap and water. Handwashing is essential because alcohol sanitizer shouldn't replace soap and water for norovirus control.

    For food- or mouth-contact surfaces, follow the disinfectant label and rinse with plain water before reuse when the label or public-health guidance calls for rinsing. Don't return dishes, utensils, or food containers to service just because they look clean.

    Laundry, Soft Surfaces, and the Tools You Used to Clean

    Soft materials need a slower approach because they can hold contamination in folds, seams, and absorbent fibers. Put on gloves, lift contaminated clothing or bedding carefully, and don't shake it. Shaking can spread material onto nearby surfaces.

    Remove solid waste into the toilet where possible, then place the laundry in a bag or directly into the washing machine. Keep it separate from other household loads until washed. Use detergent, the longest suitable cycle, and the warmest temperature the fabric can safely tolerate. Add chlorine bleach only when the care label permits it. An oxygen-based bleach alternative may be appropriate for fabrics that can't tolerate chlorine, but it shouldn't be treated as an automatic substitute for a product specifically labeled for norovirus.

    Carpets and upholstery require material-specific care. Cover wet contamination with absorbent disposable material, remove the material carefully, then use a suitable carpet cleaner or upholstery method. Steam treatment may be appropriate for compatible materials, but don't apply heat or moisture to a surface unless the manufacturer permits it.

    The tools are part of the contamination zone

    A reusable mop head, cloth, scrub brush, or bucket can redistribute virus after the visible spill is gone. Soak compatible reusable tools in a fresh 1,000 to 5,000 ppm bleach solution for at least 5 minutes, then rinse and launder or dry them according to their material and care instructions.

    Wash mop heads in a separate hot laundry cycle. High-heat drying adds another protective step when the item can tolerate it. Empty and disinfect buckets, handles, and any reusable brush that touched the contaminated area. Prepare a fresh bleach solution rather than saving a diluted mixture for another cleanup day.

    Item type Recommended treatment Temperature or concentration Contact time
    Bedding and clothing Wash separately with detergent Warmest fabric-safe setting Follow the wash-cycle and product directions
    Bleachable fabric Add chlorine bleach if the care label allows CDC norovirus range, 1,000 to 5,000 ppm for applicable surfaces At least 5 minutes for surface disinfection
    Non-bleachable fabric Wash with detergent and use an oxygen-based alternative when suitable Warmest fabric-safe setting Follow product directions
    Mop heads and cloths Soak or disinfect, then launder separately Fresh 1,000 to 5,000 ppm solution At least 5 minutes
    Buckets and scrub brushes Clean, then disinfect compatible surfaces Appropriate labeled disinfectant Follow the label

    If the volume of laundry is too much to manage safely, a professional service can reduce handling at home. Some households may choose to subscribe to wash and fold for routine laundry after contaminated items have been isolated and handled according to the service's policies. For detergent logistics and household laundry supplies, see this guide to bulk laundry pods.

    Electronics require restraint. Don't pour bleach or liquid disinfectant onto phones, remotes, keyboards, or control panels. Remove visible soil with a compatible method, then use a product whose label specifically permits the device's surface and follow its contact-time instructions.

    Why Alcohol and Most Wipes Fail Against Norovirus

    A wipe can be convenient and still be the wrong tool. Alcohol wipes, hand sanitizer, dish soap, and many general-purpose disinfecting wipes don't reliably kill norovirus, according to the Cleveland Clinic's norovirus cleanup guidance. They may remove residue or reduce contamination, but appearance isn't proof of inactivation.

    The reason is structural. Norovirus is non-enveloped, so it doesn't have the lipid outer coating that alcohol-based products commonly disrupt. That makes alcohol an unreliable choice for environmental norovirus disinfection, even when the product feels strong or evaporates quickly.

    A generic quat-based wipe also isn't automatically suitable. Look for an EPA registration and a label claim for norovirus or an accepted norovirus surrogate. The EPA List G framework exists so users can distinguish a product registered for this use from a wipe marketed only for ordinary bacteria or general household germs.

    Choosing an option for sensitive surfaces

    Bleach can discolor fabrics, corrode some metals, damage electronics, and harm certain countertop finishes. Don't force a bleach solution onto a material that the manufacturer says can't tolerate it.

    For a sensitive surface, select an EPA-registered product whose label permits that material and states the required contact time. Some accelerated hydrogen peroxide formulations may be suitable, but the label controls. A product with 3% hydrogen peroxide may be discussed for certain sensitive surfaces, yet it still needs full label contact time and material compatibility. Never combine it with bleach or another cleaner.

    The practical trade-off is straightforward. Bleach is widely available and supported by CDC guidance for compatible hard surfaces. A List G product may be easier to apply to a particular finish, but it still requires careful label reading, complete wet coverage, and the full contact time.

    Ventilation, Timing, and Knowing When the Home Is Safe Again

    Cleaning the room removes contamination from surfaces, but household behavior determines whether the virus returns to clean areas. Keep the sick person away from shared spaces as much as practical, use a separate bathroom when possible, and disinfect high-touch fixtures regularly during an active illness.

    Continue strict handwashing with soap and water. Hand sanitizer is not a dependable replacement for washing hands after caring for someone with suspected norovirus, using the toilet, changing contaminated laundry, or handling cleanup waste.

    People can remain infectious after symptoms improve. A cautious household rule is to keep the person away from food preparation and shared group settings for at least 48 hours after vomiting and diarrhea stop, consistent with public-health advice summarized by BSW Health's stomach-virus guidance. Follow local school, workplace, healthcare, and public-health policies when they are stricter.

    Ventilate during cleanup and afterward when possible, but don't direct fans across the contaminated area toward another room. Reopen the kitchen only after food-contact surfaces have been cleaned, disinfected with a compatible labeled product, and rinsed when required. Wash dishes and utensils thoroughly before sharing them again.

    A home is ready for normal use when the contamination has been removed, treated surfaces have completed their contact time, reusable tools have been handled, and no visibly soiled areas remain.

    Look for practical warning signs rather than relying on smell alone. Lingering visible soil, another household member developing vomiting or diarrhea, or an overlooked towel, handle, or floor section means the response needs another review. People with weakened immune systems, older adults, infants, and young children deserve a lower threshold for medical advice if symptoms or dehydration become concerning.

    For more detail on the distinction between airborne spread, droplets, and contaminated surfaces, see whether stomach viruses are airborne.

    A six-step infographic guide on ventilation, timing, and recovery protocols for ensuring a safe home environment.

    Quick Reference Checklist and Common Follow-Up Questions

    Use this list when you're tired and need the essentials in front of you:

    • Protect yourself: Put on gloves, use a face covering when splashing or aerosol exposure is possible, and isolate the room.
    • Remove first: Collect vomit or stool with disposable towels and seal the waste.
    • Clean before disinfecting: Use detergent and water to remove organic material.
    • Use the right chemistry: Choose a CDC-recommended bleach solution in the 1,000 to 5,000 ppm range or an EPA-registered norovirus product.
    • Respect contact time: Keep the disinfectant visibly wet for at least 5 minutes.
    • Treat the wider zone: Wipe handles, switches, faucets, toilet fixtures, and nearby objects.
    • Clean the tools: Disinfect mop heads, cloths, brushes, buckets, and other reusable equipment.
    • Wash hands: Use soap and water after removing gloves and finishing cleanup.

    How long does norovirus survive on surfaces? It can remain on hard surfaces for days, so clean and disinfect rather than waiting for the area to “air out.”

    Is someone still infectious after 48 hours without symptoms? Yes, transmission can still be possible. Keep handwashing and food-safety precautions in place, and follow the isolation guidance above.

    When can people share a bathroom? After contaminated surfaces and touchpoints have been cleaned and disinfected, with no visible soil remaining. Continue cleaning frequently while illness is active.

    What about kitchen food? Discard visibly contaminated food, clean and disinfect food-contact surfaces with a compatible labeled product, and rinse when required before preparing food again.

    Can pets carry it? Keep pets away from vomit, stool, bags, and cleaning chemicals. Don't let an animal track through a contaminated area before it has been cleaned.

    For mattresses, bedding, and bedroom fabrics, this practical guide to mattress care for spring cleaning can help you identify soft surfaces that deserve attention after the bathroom is finished.

    The critical details are simple but easy to skip: remove organic matter, use a verified norovirus disinfectant, keep it wet long enough, and disinfect the equipment that did the cleaning.


    If a stomach-virus incident has just happened, isolate the area, gather gloves and disposable towels, and check the disinfectant label before you start. For additional virus-specific cleanup and prevention guidance, visit VirusFAQ.com and use the relevant norovirus resources alongside current CDC and EPA directions.

  • Does Hand Sanitizer Kill Norovirus: What You Need to Know

    No, regular hand sanitizer isn't reliable against norovirus. In controlled hand studies, alcohol-based products have produced reductions ranging from 0.14 to 0.34 log10, while soap and water used for 20 seconds reduced norovirus by 0.7 to 1.2 log10 in CDC-cited finger-pad studies.

    That challenges one of the most popular hygiene assumptions: that sanitizer kills every virus equally well. It doesn't. Norovirus has a structure that makes alcohol-based products less dependable, so using sanitizer after bathroom use or before eating can create false confidence. Soap and running water remain the preferred defense, with sanitizer serving only as an adjunct when washing isn't available.

    The Truth About Hand Sanitizer and Norovirus

    Hand sanitizer works well for some germs, but that doesn't mean it works equally well for all viruses. Norovirus is a major exception. The CDC's norovirus prevention guidance states that hand sanitizer “does not work well against norovirus” and recommends washing with soap and water for at least 20 seconds.

    That distinction matters in ordinary situations. After using the bathroom, changing a diaper, cleaning vomit, or handling a contaminated surface, sanitizer alone may leave enough virus on your hands to pose a transmission risk. Norovirus spreads when contaminated material reaches the mouth, often through hands that appear clean.

    An infographic explaining that hand sanitizer is not a reliable defense against the norovirus infection.

    What CDC guidance means in practice

    CDC guidance doesn't say sanitizer is useless in every circumstance. It says sanitizer shouldn't replace handwashing for norovirus. During outbreaks, CDC recommends soap and water after patient contact, while alcohol-based sanitizer may be considered for other hand-hygiene indications, not as a proven stand-alone norovirus control.

    The practical decision is straightforward:

    • After bathroom use: Wash with soap and water, even if sanitizer is nearby.
    • Before eating or preparing food: Wash thoroughly at a sink.
    • During an outbreak: Treat handwashing as essential, particularly after caring for someone who is ill.
    • Without immediate access to a sink: Use sanitizer as a temporary adjunct, then wash as soon as possible.

    Practical rule: Sanitizer can fill a gap between handwashing opportunities, but it shouldn't erase the need to wash.

    The same principle applies when comparing this question with broader virus guidance. VirusFAQ's guide to whether hand sanitizer kills viruses explains why product performance depends on the virus, its outer structure, the formulation, and how the product is used.

    Norovirus also resists many standard disinfection approaches because it's a non-enveloped virus. Alcohol can be highly useful against some enveloped viruses, but norovirus requires a prevention strategy centered on physical removal and appropriate environmental disinfection.

    Why Norovirus Resists Alcohol-Based Sanitizers

    The simplest virology lesson is also the most useful one: viruses aren't built alike. Influenza viruses and coronaviruses have lipid envelopes, which are relatively vulnerable to substances that disrupt fatty membranes. Norovirus lacks that envelope and instead carries its genetic material inside a tough protein shell called a capsid.

    Noroviruses are approximately 27 to 38 nanometers in diameter and are classified as non-enveloped viruses. A Scientific Reports study on alcohol and human norovirus describes how the absence of a lipid envelope contributes to resistance against alcohol-based sanitizers, low-level detergents, and some standard disinfection protocols.

    A 3D model of a norovirus capsid next to a bottle of alcohol-based hand sanitizer.

    The capsid changes the cleaning problem

    An alcohol gel can disrupt the envelope of certain viruses. Norovirus presents a different target. Its protein capsid remains stable across a range of environmental conditions, including different pH levels, and the virus can persist on surfaces and in water.

    That stability helps explain why a contaminated bathroom handle, tap, phone, or countertop can remain a concern after an illness episode. The virus doesn't need to be visible to move from a surface to a hand, and a hand doesn't need to look dirty for transmission to occur.

    The issue isn't just that alcohol is “weak.” The product is being asked to work against a virus with a more resistant outer structure. Formulation, exposure time, soil on the hands, and the amount of contamination all influence the result.

    Surface control requires a different response

    Hand hygiene addresses one route of transmission, but it doesn't clean the environment. Vomiting and diarrhea can contaminate nearby surfaces, while routine touching redistributes particles to fixtures and objects.

    For that reason, a person can wash correctly and still become exposed by touching a contaminated surface immediately afterward. Effective prevention pairs handwashing with appropriate surface cleaning, especially in bathrooms, kitchens, care settings, and shared spaces.

    This doesn't mean you need to treat every object as dangerous. It means you should change your routine when someone has symptoms. Prioritize surfaces that people touch frequently and follow the label directions for any disinfectant, including the time the surface must remain visibly wet.

    Understanding Mixed Research Findings

    Readers can find laboratory studies that sound more optimistic than public-health advice. That apparent contradiction usually comes from differences in the test system, the product formulation, the exposure conditions, and what researchers measure.

    The 2020 Scientific Reports research found that ethanol or isopropanol could sufficiently suppress replication of GII.4 human norovirus in human intestinal epithelial cells under specific laboratory conditions. GII.4 causes the majority of epidemic human norovirus infections worldwide, but a result in cultured cells doesn't automatically show that a sanitizer will prevent illness on a person's hands during an outbreak.

    A reduction isn't the same as elimination

    Researchers often report changes using log10 reductions. A reduction means the measured amount of virus or viral material became lower under the test conditions. It doesn't necessarily mean that every infectious particle disappeared or that the product prevented transmission in daily life.

    One human-hand study found that an alcohol-based sanitizer reduced norovirus genomic copies by only 0.14 to 0.34 log10, with an average of 0.27 ± 0.12 log10. That is a small reduction compared with the stronger removal expected from a dependable disinfection method, and it doesn't support treating sanitizer as a replacement for washing.

    More recent volunteer studies found that some high-ethanol products reduced human norovirus on fingerpads by about 2.4 to 3.3 log10, while a benchmark 60% ethanol product achieved 1.7 ± 0.5 log10. None completely eliminated detectable virus. These results show that some formulations may reduce contamination substantially, but they also show why product-to-product performance can't be assumed.

    Why the laboratory and CDC conclusions can coexist

    Another laboratory study using a human intestinal enteroid model found that 60% ethanol produced less than a 1 log10 reduction in viral genome equivalents after 30 or 60 seconds. Two commercial alcohol-based sanitizers produced larger 2.2 to 3.2 log10 reductions in suspension assays, yet residual replication remained after 60 seconds. The findings point to wide variation among formulations and test conditions.

    A laboratory may apply a measured amount of product to a defined sample under controlled pH, contact time, and contamination conditions. Everyday hand hygiene is less controlled. Hands may contain organic material, the sanitizer may not cover every surface, and the user may touch another object immediately afterward.

    A promising laboratory reduction answers, “Can this formulation lower measured virus under these conditions?” Public guidance asks a broader question: “Can people rely on it to prevent infection in real settings?” Those aren't the same test.

    This is why CDC guidance remains cautious. Some products may show activity in particular assays, but the practical conclusion is unchanged: sanitizer isn't a reliable stand-alone defense against norovirus. It may reduce risk when washing isn't possible, but soap and water remain the safer primary measure.

    Proper Hand Hygiene When Norovirus Threatens

    The most dependable response is mechanical removal. Soap loosens material from the skin, rubbing helps cover the hands and dislodge contamination, and running water carries it away. That approach doesn't depend on alcohol penetrating a resistant viral capsid.

    CDC recommends washing with soap and water for at least 20 seconds. The CDC updated norovirus guideline reports that 20 seconds of soap-and-water washing reduced norovirus by 0.7 to 1.2 log10 in finger-pad studies, while alcohol-based sanitizers didn't show the same reduction.

    An infographic showing four steps for proper hand hygiene to effectively prevent the spread of norovirus.

    A reliable washing routine

    1. Wet your hands and apply soap. Use enough soap to cover the palms, backs of the hands, fingers, thumbs, and around the nails.

    2. Rub every surface for at least 20 seconds. Interlace your fingers, scrub between them, rub the backs of your hands, and rotate each thumb. Pay attention to fingertips because they frequently contact the mouth and food.

    3. Rinse under running water. Let the water carry loosened material away rather than just wiping the hands with a towel.

    4. Dry thoroughly. A disposable towel can reduce contact with a shared hand-drying surface and can help you turn off a tap without touching it directly.

    The proper hand-washing technique guide provides a useful visual reference for covering the areas people often miss. If you're choosing supplies for a healthcare, hospitality, or food-service setting, information about antibacterial soap from Simply Hospitality can help you compare available hand-soap options. The key protection against norovirus still comes from thorough washing and rinsing, not from assuming that an antibacterial label guarantees norovirus control.

    When sanitizer has a role

    Sanitizer is reasonable as a temporary measure when there's no sink. Apply it to all hand surfaces according to the product label, avoid treating it as a completed norovirus hygiene step, and wash with soap and water at the first opportunity.

    After bathroom use, before eating, and after contact with vomit or fecal material, prioritize a sink. In healthcare settings during a norovirus outbreak, CDC guidance specifically prioritizes soap and water after patient contact.

    Comparing Disinfection Methods for Norovirus Control

    Hands and surfaces need different interventions. Hand sanitizer is designed for use on skin, while disinfectants are formulated for objects and environmental surfaces. A product that is appropriate for a countertop may be unsafe for hands, so never substitute a surface disinfectant for hand hygiene.

    For environmental cleaning, select a product whose label specifically supports use against norovirus or an accepted surrogate, and follow the label's required wet contact time. Spraying a surface and wiping it immediately may remove some contamination, but it may not provide the labeled disinfection effect.

    Method Effectiveness Best Use Case
    Soap and water Preferred method for removing norovirus from hands; CDC-cited finger-pad studies found a 0.7 to 1.2 log10 reduction after 20 seconds Hands after bathroom use, caregiving, food preparation, or suspected exposure
    Bleach-based disinfectant Use only when the product label identifies the appropriate norovirus claim and gives directions for dilution and contact time Hard, non-porous bathroom and household surfaces
    Commercial disinfectant wipes Performance depends on the formulation, label claim, coverage, and required wet contact time High-touch hard surfaces when the product is labeled for norovirus control
    Alcohol-based hand sanitizer Not reliable as a stand-alone norovirus defense; some formulations show variable laboratory reductions Temporary adjunct when soap and water aren't immediately available
    Quaternary ammonium compounds Don't assume effectiveness from the chemical category alone; verify the product label and norovirus claim Surfaces only, where the label specifically permits the intended use

    A wipe can be convenient, but convenience doesn't remove the need for complete coverage. Keep the surface visibly wet for the stated contact time, then follow any rinsing or ventilation instructions. For households with animals, guidance on how to clean with pets in mind can help you consider ingredient exposure and surface safety without confusing pet-safe cleaning with proven norovirus disinfection.

    Surface rule: Choose by the product label and intended surface, not by the word “sanitizer” alone.

    Bathrooms and frequently touched fixtures deserve particular attention after vomiting or diarrhea. Food-contact surfaces may require a rinse after disinfection, depending on the label. Soft furnishings, carpets, and porous materials need special handling because a standard hard-surface wipe may not be suitable.

    The norovirus disinfection guide offers a practical reference for matching cleaning steps to the environment. If someone is actively ill, limit unnecessary contact with contaminated areas and clean according to public-health or healthcare-facility procedures when applicable.

    Building a Complete Norovirus Prevention Strategy

    No single hygiene product creates complete protection. A durable plan combines handwashing, surface disinfection, and outbreak awareness, because each addresses a different route of exposure.

    A visual guide outlining three key Norovirus prevention strategies: hand hygiene, surface disinfection, and outbreak awareness.

    At home, make the sink the default after bathroom use and before meals. During illness, separate the sick person's towels and supplies, clean high-touch surfaces with a labeled disinfectant, and avoid preparing food for others while symptomatic.

    In workplaces, schools, care facilities, and hospitality settings, reinforce handwashing access and respond quickly to vomiting or diarrhea. During a known outbreak, follow the relevant local or institutional infection-control guidance rather than relying on sanitizer stations alone.

    For travel, carry sanitizer for situations where washing isn't immediately possible, but plan around access to soap and running water. A small cleaning kit for personal high-touch items can support the broader routine, but it shouldn't turn every journey into a contamination ritual.

    If symptoms occur, focus on fluids and watch for dehydration. Seek medical advice when symptoms are severe, persistent, or concerning, especially for children, older adults, or people with weakened immune systems.


    If you need to make one change today, replace sanitizer-only hand cleaning after bathroom use with 20 seconds of soap-and-water washing. Then review the disinfectant labels in your home, workplace, or travel kit and choose a surface product that specifically addresses norovirus, using its full contact-time instructions.

  • Ebola Virus Characteristics and Prevention

    Ebola disease has produced case-fatality proportions ranging from 25% to 90%, with an average around 50%, yet its transmission depends on a much narrower route than casual proximity. According to the World Health Organization's Ebola disease fact sheet, infected people don't transmit the disease during incubation. Transmission generally begins when symptoms appear and occurs through direct exposure to blood or other body fluids.

    That contrast defines the most useful way to understand Ebola virus characteristics. Ebola can cause severe, systemic illness, but it isn't an invisible airborne threat that spreads only because people share a room. Its biology, clinical progression, species differences, and environmental behavior determine where prevention efforts should focus. Surface cleaning is one part of a wider response that also includes rapid recognition, isolation, protective equipment, safe care, contact tracing, and safe burials.

    Understanding the Core Ebola Virus Characteristics

    Ebola disease comes from viruses in the genus Orthoebolavirus, part of the Filoviridae family. Six orthoebolavirus species have been identified, and three are known to cause large outbreaks: Ebola virus, Sudan virus, and Bundibugyo virus. “Ebola” therefore describes a related group, not one perfectly uniform pathogen. That distinction helps explain why vaccines, treatments, and fatality patterns can differ between outbreaks.

    The incubation period is typically 2 to 21 days. People are not considered infectious until symptoms begin, according to the WHO clinical overview. Someone may have been exposed, feel well, and still need careful monitoring. Once illness starts, however, the risk assessment changes because body fluids can carry the virus.

    What drives transmission

    Ebola most commonly spreads through direct contact with blood, vomit, sweat, saliva, and other body fluids from a symptomatic patient. Exposure may occur while caring for someone who is ill, touching contaminated materials, or handling a body after death without appropriate infection-control measures.

    The route is dangerous but defined. Casual proximity alone isn't the central transmission mechanism, and walking past an infected person before symptoms appear does not by itself create the same risk as fluid contact. Risk increases when fluids reach damaged skin or mucous membranes, especially during close care or cleanup without suitable protection. The CDC's Ebola transmission guidance also emphasizes contact with infected blood or body fluids as the primary route.

    That practical boundary matters for prevention. The virus can produce severe systemic disease inside the body, yet its environmental fragility makes rigorous cleaning and disinfection of contaminated surfaces a practical circuit-breaker outside it.

    Practical rule: Treat any suspected infectious fluid as hazardous, and leave assessment, testing, isolation, and clinical care to trained public health and medical teams.

    Why the fatality range needs context

    Reported fatality has fallen in outbreaks with early supportive care, while the 25% to 90% WHO range reflects settings with differing clinical capacity. Outcomes also vary with the virus species, speed of recognition, access to supportive care, infection-control systems, and the circumstances of the outbreak.

    The most useful mental model is a severe infection with defined biological constraints. Prevention works when responders identify cases early, limit fluid exposure, disinfect contaminated environments correctly, and interrupt contact chains. That focus connects Ebola's frightening pathology with practical actions that can reduce transmission.

    Morphology and Genomic Architecture

    A diagram illustrating the connection between morphological traits and genomic architecture in biological organisms.

    Ebola virions are slender, threadlike particles. Under an electron microscope, their distinctive filamentous shape reflects an enveloped structure wrapped around a helical nucleocapsid. Approximate dimensions are 80 nanometers in diameter and 970 to 1200 nanometers in length, as described in the AABB technical reference on Ebola virus.

    The envelope is a lipid membrane surrounding the viral core. It helps the virion attach to and enter susceptible host cells, while also leaving the particle dependent on the envelope's physical integrity. Heat, drying, environmental conditions, and suitable disinfectants can damage enveloped viruses more readily than many non-enveloped viruses. The broader principle is explained in viral envelope biology.

    The genome works like a compact instruction set

    Ebola virus is a non-segmented, negative-sense RNA virus. Its genome is about 19 kb and contains 7 genes that produce 9 proteins, according to the Journal of Leukocyte Biology review.

    “Negative-sense” means host ribosomes cannot read the genome directly as messenger RNA. The virus first needs to produce a readable RNA copy. It therefore packages its own RNA-dependent RNA polymerase machinery inside the virion, supplying the tools needed to begin transcription and genome synthesis after entry into a susceptible cell.

    This compact arrangement helps explain Ebola's acute infection pattern. The virus arrives with the machinery required to start replication rather than relying on a dormant genetic program that later reactivates. Clinical reviews also do not describe a carrier state comparable to the lifelong latency associated with some other viruses.

    Structure connects to prevention

    The lipid envelope supports cell entry, yet it also creates a practical weakness outside the host. Rigorous disinfection can disrupt contaminated material on frequently touched surfaces. It does not replace clinical isolation, protective equipment, or trained handling, but it can interrupt an environmental contact route.

    Protect the patient, protect the caregiver, and remove infectious material from the environment. Effective disinfection requires a product approved for the intended pathogen or setting, careful adherence to its label, and enough wet contact time for the product to work. The terrifying systemic effects of Ebola begin inside the body, while its fragile outer structure gives everyday cleaning a concrete role in breaking transmission.

    Transmission Dynamics and Environmental Persistence

    Ebola transmission is best understood as a chain. A symptomatic person sheds virus in infectious body fluids. Another person encounters those fluids through care, cleaning, medical procedures, funeral practices, or contaminated materials. The chain continues only if the exposure reaches a susceptible person and infection-control measures fail to stop it.

    This explains why outbreak control uses several safeguards at once. Health teams identify suspected cases, arrange testing, isolate patients, monitor contacts, provide clinical care, use protective equipment, and manage bodies safely. Cleaning contaminated surfaces adds another barrier, especially in treatment areas, homes, transport settings, and facilities where people handle equipment or bodily fluids.

    The environmental route is practical, not magical

    A contaminated surface doesn't independently create an outbreak. It becomes relevant when infectious material reaches it and another person later touches that material, then touches their eyes, nose, mouth, broken skin, or protective equipment incorrectly. The exact risk depends on the amount and condition of contamination, the surface, handling practices, and the effectiveness of cleaning.

    That's why routine visual tidiness isn't enough in a suspected exposure setting. Trained personnel need a defined process for spill management, waste handling, reusable equipment, laundry, and disinfection. Household members shouldn't attempt to care for a suspected patient without guidance from health authorities.

    Exposure control works as a chain of barriers. If one barrier fails, isolation, protective equipment, hand hygiene, and environmental disinfection can still prevent the next exposure.

    Recovery doesn't erase every biological question

    Recent reviews describe a more complex recurrence pattern. The review of survivor-linked Ebola recurrence notes that the 2021 Guinea outbreak established survivor-linked recurrence as a transmission pattern, with genetically identical Ebola virus persisting in an immune-privileged site for over five years after recovery.

    This finding doesn't mean recovered people are generally contagious or that ordinary contact with survivors is unsafe. It means public health teams must account for rare, biologically plausible persistence in protected body sites when investigating an unexpected re-emergence. Survivor care, clinical follow-up, sensitive communication, and genomic investigation all matter.

    Symptom-based screening remains useful because people aren't infectious during incubation, but it can't answer every outbreak question by itself. Transmission patterns also depend on illness severity, the intensity of contact, caregiving practices, and the possibility of persistence in survivors.

    Incubation Period and Clinical Manifestations

    After exposure, Ebola disease usually begins after an incubation period of 2 to 21 days, with symptoms averaging 8 to 10 days after contact, according to the CDC Health Alert Network notice. During incubation, infected people aren't considered contagious. Once symptoms begin, the situation changes, and suspected illness requires immediate medical and public health attention.

    Early symptoms can resemble other infections. Fever, weakness, headache, muscle pain, gastrointestinal symptoms, and abdominal discomfort may appear before severe disease becomes obvious. Bleeding is widely associated with Ebola in popular culture, but it isn't the only or even the defining early sign. A clinician must consider exposure history, local outbreak conditions, symptom progression, and appropriate laboratory testing.

    An educational infographic illustrating the timeline of illness progression, from exposure through incubation to common clinical symptoms.

    Why severe illness becomes systemic

    Ebola pathogenesis involves far more than direct destruction of infected cells. The clinical pathogenesis review describes a connected process involving intense immune suppression, abnormal inflammatory signaling, endothelial dysfunction, coagulopathy, and progressive multiorgan injury.

    The endothelium lines blood vessels. When vascular regulation becomes impaired, fluid balance and circulation can deteriorate. Coagulation abnormalities can contribute to bleeding and tissue injury, while inflammatory and immune disturbances can worsen damage across multiple organs.

    A patient may therefore move from apparently nonspecific illness to profound weakness, fluid loss, circulatory instability, and organ dysfunction. The clinical priority isn't to wait for dramatic hemorrhage. It's to recognize risk early and monitor the systems most likely to fail.

    What care teams need to watch

    Severe disease requires careful attention to:

    • Fluid and electrolyte loss: Vomiting and diarrhea can rapidly undermine circulation and organ function.
    • Coagulation changes: Abnormal clotting can contribute to bleeding and vascular injury.
    • Kidney and liver function: Multiorgan injury can alter laboratory findings and medication decisions.
    • Circulatory status: Vascular dysfunction and fluid depletion can produce shock-like deterioration.
    • Infection-control needs: Every clinical interaction must protect staff, other patients, caregivers, and the wider community.

    Early care can improve the chance of a better outcome, but suspected Ebola is a medical emergency. People shouldn't self-test, handle potentially contaminated materials, or travel through public spaces seeking informal advice. Contact local health services first and follow their instructions.

    Species Variations and Historical Outbreak Context

    Ebola is not one uniform virus. Related orthoebolavirus species differ in documented fatality patterns, available countermeasures, and outbreak-control requirements. The New England Journal of Medicine perspective on species-specific Ebola response explains that approved vaccines currently target Ebola virus, also called Zaire ebolavirus. No approved vaccine or therapeutic agent exists for Bundibugyo virus disease, while the 2025 Uganda trial focused on Sudan virus because licensed protection for non-Zaire species remains limited.

    Species identification therefore affects decisions from the beginning. Laboratory confirmation, and genomic characterization where available, can show whether a vaccine or treatment developed for one species is relevant to the outbreak at hand.

    Comparison of Primary Orthoebolavirus Species

    Species Historical Fatality Range Approved Vaccine Availability
    Ebola virus, Zaire ebolavirus 25% to 90% across Ebola outbreaks, as reported in the historical benchmark below Approved vaccine available
    Sudan virus About 40% to 65% in documented outbreaks, according to the NEJM species-response perspective No approved vaccine
    Bundibugyo virus About 25% in the 2007 to 2008 DRC outbreak, according to the CDC MMWR historical account No approved vaccine

    These figures describe historical outbreaks, not a guaranteed outcome for every patient or future event. They show why risk, countermeasures, and outbreak control differ by species.

    The historical benchmark

    The largest Ebola outbreak occurred in West Africa from 2014 to 2016. It caused 28,610 cases and 11,308 deaths across 10 countries, with a case fatality proportion of about 40%, according to the CDC MMWR historical account. Delayed case detection and limited health-system capacity allowed transmission to expand across communities and borders.

    Ebola was first identified in 1976. Outbreaks have remained concentrated mainly in sub-Saharan Africa, where natural reservoirs can occasionally enable spillover into humans. The West African epidemic became a defining benchmark because its death toll exceeded that of all earlier outbreaks combined by more than tenfold.

    A 2025 DRC outbreak caused by Zaire ebolavirus was rapidly contained with more than 47,500 vaccinations. Sudan and Bundibugyo outbreaks, by contrast, showed the practical limits of species-specific protection. Preparedness begins with recognizing Ebola, then determining which Ebola virus is involved.

    Surface Disinfection and Prevention Strategies

    Ebola's lipid envelope is the most useful structural fact for prevention: correctly applied disinfection can disrupt this outer layer and interrupt contamination on suitable surfaces. The virus can cause severe systemic disease in a person, yet its environmental weakness makes careful cleaning a practical circuit-breaker for transmission.

    “Wipe the surface” is not a complete protocol. Choose a disinfectant approved for the setting, manage visible contamination according to the facility's procedure, and keep the surface wet for the label-specified contact time. Staff also need gloves, eye protection, gowns, and masks or respirators where indicated, along with training for spills and waste.

    A checklist infographic titled Surface Disinfection and Prevention Strategies showing best practices for cleaning and disinfecting.

    A safer cleaning sequence

    1. Restrict access: Keep unprotected people away from suspected contamination.
    2. Put on appropriate protection: Follow the protective-equipment requirements set by trained infection-prevention personnel.
    3. Remove visible contamination safely: Organic material can reduce disinfection performance, so use the facility's approved spill procedure.
    4. Apply the correct disinfectant: Select a product authorized for the intended pathogen and surface.
    5. Respect contact time: Keep the surface wet for the full label instruction. Drying it too soon can reduce effectiveness.
    6. Dispose of materials correctly: Treat used wipes, gloves, and other contaminated items as regulated infectious waste where applicable.
    7. Perform hand hygiene: Clean hands after removing protective equipment and handling waste.

    Disinfecting wipes suit controlled, small-area cleaning because they deliver a measured amount of product without requiring a spray that could spread droplets or aerosolize contamination. They still require careful selection and label use. Follow institutional guidance, and never mix chemicals.

    High-risk work involving blood or body fluids requires procedures beyond ordinary household cleaning. Guidance on forensic pathologist safety precautions illustrates why trained personnel use specialized protective measures.

    Prevention starts before the surface

    Environmental disinfection works alongside early reporting, isolation, contact monitoring, safe patient transport, and professional management of bodies after death. Family members should avoid touching a sick person's blood, vomit, diarrhea, saliva, sweat, or bedding, then contact public health authorities for instructions.

    For product-selection principles and virus-focused cleaning considerations, see this comparison of disinfectants effective against enveloped and non-enveloped viruses. No consumer product replaces emergency guidance when Ebola is suspected.

    Cleaning is a circuit-breaker, not a diagnosis. Use it to interrupt contamination after trained responders establish a safe plan.

    Key Takeaways for Public Health and Safety

    Ebola's most important characteristics form a connected pattern. It's an enveloped, filamentous, negative-sense RNA virus with a compact genome. It causes acute disease through systemic immune, vascular, coagulation, and organ disturbances. It usually spreads through direct exposure to body fluids from symptomatic people, not through casual proximity during incubation.

    The practical implications are clear:

    • Recognize symptoms in context: Fever, weakness, gastrointestinal illness, and worsening systemic signs require urgent professional assessment when exposure is possible.
    • Don't handle fluids or contaminated materials casually: Blood, vomit, sweat, saliva, and other body fluids can create exposure risk once illness begins.
    • Use layered controls: Isolation, protective equipment, hand hygiene, testing, contact monitoring, clinical support, and safe burials work together.
    • Clean deliberately: Use a suitable disinfectant, follow the label, maintain contact time, and dispose of wipes and protective materials safely.
    • Respect species differences: A vaccine or treatment designed for Zaire ebolavirus shouldn't be assumed to work against Sudan or Bundibugyo virus.

    The most frightening feature of Ebola is its potential for severe systemic disease. The most useful feature for prevention is that transmission follows identifiable routes. Public health teams can break those routes by finding cases early, protecting caregivers, managing fluids safely, and removing contamination from the environment.

    If you're building a reliable reference library for virus biology, transmission, and prevention, visit VirusFAQ.com for accessible educational and scientific articles, then share this Ebola guide with healthcare educators, students, and community teams who need clear, evidence-based information.

  • Virology for Beginners: A Practical Guide

    You touch a restaurant door handle, adjust your phone, and reach for a sandwich. Later, someone mentions a “viral outbreak,” and an ordinary moment suddenly feels threatening. Virology for beginners offers a calmer way to understand that risk: viruses aren't random clouds of bad luck. They're biological particles with particular structures, entry points, transmission routes, and weaknesses.

    This field became a recognized scientific discipline in 1898, when Friedrich Loeffler and Paul Frosch showed that foot-and-mouth disease could pass through a filter that stopped bacteria, providing clear evidence for a smaller infectious agent (historical overview of virology). Once you understand the rules, sensible prevention becomes much easier than guessing.

    The Hidden World Living on Your Doorknob

    You grasp a smooth handrail at the gym. At a restaurant, you push open a door, pull out a chair, and handle a menu before eating. Those surfaces may have contacted many hands, but the important question isn't whether every object is dangerous. It's which virus might be present, how long it can remain infectious, and whether it can reach a suitable entry site.

    A person's hand gently reaching out to touch a smooth, silver metal railing in a bright room.

    Virology studies viruses, the tiny infectious particles that depend on living cells to reproduce. Bacteria are complete cells with their own internal machinery. A virus is closer to an encrypted USB drive: it carries instructions, but it needs your body's “computer,” a host cell, to unpack those instructions and manufacture new particles.

    That dependence explains why viruses are not just miniature bacteria. Most viruses contain genetic material inside a protein shell, and many animal viruses also have a lipid envelope borrowed from a host-cell membrane (virus structure and environmental stability). Their size is commonly measured in nanometres, far below what ordinary light microscopy can resolve.

    From fear to useful questions

    Hearing “viral outbreak” often triggers a broad fear of contamination. A better response is to ask focused questions:

    • What virus is involved? HIV-1, influenza A, SARS-CoV-2, norovirus, and hepatitis viruses don't behave alike.
    • How does it spread? Transmission may involve respiratory material, blood, contaminated food or surfaces, sexual contact, or insects.
    • What protects it outside the body? An envelope, or lack of one, changes its sensitivity to drying, detergents, alcohol, and disinfectants.

    The world's viral threats illustrate that range. WHO estimates that more than 3.9 billion people in over 132 countries are at risk of dengue, with about 96 million symptomatic cases and around 40,000 deaths each year (WHO information on vector-borne diseases). Viral hepatitis B and C affect about 325 million people globally, while hepatitis C caused an estimated 1.75 million new infections in 2015, according to the same WHO source.

    Understanding those differences replaces vague alarm with practical judgment. For surface questions, consult this guide to how long viruses live on surfaces, then match your precautions to the actual route of exposure.

    Anatomy of a Virus, Capsids, Envelopes, and Surprises

    Think of a virus as a sneaker packaged for delivery. The genetic material is the instruction set. The capsid is the protective protein container around it. Some viruses add an envelope, a fatty outer layer that helps them enter certain cells but also makes them more vulnerable to environmental damage.

    A creative infographic explaining virus anatomy by comparing capsids, envelopes, and genetic material to sneaker components.

    Three parts to recognize

    1. Genetic material
      A virus carries DNA or RNA. This material contains the instructions for making viral components, but the virus can't read and execute them independently.

    2. Capsid
      The capsid is a protein shell that protects the genome. Capsids can form icosahedral, helical, or complex shapes, and their design affects stability and how viral proteins interact with host cells.

    3. Envelope
      An envelope is an optional lipid membrane. Influenza A viruses, including H1N1, H2N2, and H5N1, have envelopes. SARS-CoV-2 also has one. Soap can disrupt lipid membranes, which helps explain why thorough handwashing is useful against many enveloped viruses.

    The distinction becomes especially important when comparing enveloped viruses with non-enveloped viruses. Norovirus, human rotavirus, rhinovirus, and feline calicivirus lack that fatty outer layer. Their protein-based exterior can tolerate conditions that damage a lipid membrane, so routine alcohol products aren't automatically reliable against them.

    Structural clue: An envelope can help a virus enter a cell, but it can also make the particle easier to disrupt outside the body.

    Envelope status isn't a complete prediction of transmission. HIV-1 is enveloped and spreads through particular body fluids, not casual contact with a doorknob. Influenza A and SARS-CoV-2 are also enveloped, but their respiratory transmission patterns differ because their surface proteins, preferred receptors, tissue targets, and shedding routes differ.

    For a deeper explanation of the components and their jobs, explore virus structure and function. The central lesson is simple: a virus's hardware shapes both its biology and the cleaning method that can disable it.

    The Viral Playbook, How Infection Actually Happens

    A virus begins infection by finding a compatible host cell. Its surface molecules must attach to a receptor, much like a key fitting a particular lock. If the lock isn't present, or if the interaction is too weak, infection may fail even when the particle reaches the tissue.

    The usual sequence is orderly:

    1. Attachment connects the virus with a host-cell receptor.
    2. Penetration moves the particle or its genome across the cell boundary.
    3. Uncoating releases the genetic instructions.
    4. Genome replication and protein synthesis produce viral material.
    5. Assembly and maturation build new virions.
    6. Release sends them toward other cells.

    This cycle can involve membrane fusion for enveloped viruses, while non-enveloped viruses may enter through endocytosis or routes that disrupt a membrane. Once inside, the virus redirects host ribosomes and other biosynthetic machinery toward viral production (viral replication cycle).

    Why timing confuses people

    Exposure and symptoms don't occur at the same moment. During the incubation period, the virus may be replicating, moving through tissues, and provoking an immune response before you feel ill. A test taken very early can miss an infection if the sampled site contains too little detectable viral material.

    That doesn't mean a negative result is meaningless. It means the result answers a time-specific question: “Was enough target material present in this sample at this moment for this test to detect?” Clinicians consider symptoms, exposure history, sampling quality, and the test's purpose when interpreting the result.

    The viral playbook also explains why entry points matter. Blocking contact with the eyes, nose, and mouth, covering respiratory emissions, and avoiding contact with infected blood or secretions can interrupt the earliest stage of infection. This is not about making every environment sterile. It's about reducing the chances that a viable virus reaches the cells it can use.

    For a plain-language walkthrough of this process, see how viruses infect cells.

    Why Some Viruses Fly Through the Air and Others Don't

    “How did I catch it?” rarely has one universal answer. Viruses travel in different vehicles, and those vehicles determine which behaviours create meaningful exposure.

    Transmission route Typical setting Why the route matters
    Respiratory Shared indoor air, coughs, sneezes, close conversation The virus must leave one person's airway and reach another person's susceptible tissue
    Fecal-oral Contaminated hands, food, water, or surfaces A small lapse before eating can move particles from a contaminated object to the mouth
    Bloodborne or fluid exposure Shared needles, sexual contact, medical exposure, or infected body fluids Infection depends on direct access to susceptible tissue or bloodstream
    Vector-borne Mosquitoes and other insects The vector transfers the virus during feeding rather than through an ordinary surface

    Structure helps explain the contrast, but it doesn't replace route-specific evidence. Non-enveloped enteric viruses such as hepatitis A virus, rotavirus, and astrovirus can remain infectious on surfaces for at least 2 months, while influenza viruses have been documented for up to 48 hours on hard, non-porous surfaces and up to 12 hours on porous surfaces (review of virus persistence on surfaces).

    That difference changes priorities. A stomach-virus concern makes handwashing, food handling, bathroom hygiene, and effective surface disinfection central. A respiratory-virus concern places more emphasis on ventilation, staying away from symptomatic people, and reducing inhalation exposure.

    The route is more important than the label

    HIV-1 provides a useful corrective to surface anxiety. It is an enveloped virus, but its known transmission depends on specific infected fluids reaching vulnerable tissues. Touching an intact surface isn't equivalent to that exposure.

    H5N1, SARS-CoV-2, and seasonal influenza also require separate risk assessments. Their names may all appear in respiratory-health discussions, but host range, tissue preference, environmental stability, and the circumstances of exposure affect what prevention makes sense.

    Practical rule: Don't ask only whether a virus is “contagious.” Ask how it leaves the host, how it survives long enough to reach another person, and where it enters.

    How Doctors Catch a Stealthy Invader, Testing and Diagnosis

    A clinician choosing a viral test is matching a tool to a biological target. The sample might contain viral genetic material, viral proteins, or evidence that the immune system has responded to an earlier infection. Each approach answers a different question.

    PCR reads the genetic fingerprint

    PCR works like a highly controlled photocopier. It amplifies selected genetic material so laboratory instruments can detect it more readily. For RNA viruses, the laboratory first converts RNA into a form that can be amplified, then looks for matching sequences.

    PCR can be highly sensitive, but it still depends on the right sample, collection technique, timing, and target. A sample taken from the wrong site or too early in infection may not represent what is happening elsewhere in the body.

    Antigen tests provide a faster snapshot

    Rapid antigen tests look for viral proteins rather than copying genetic material. They can produce results quickly, which makes them useful when a person needs an immediate indication, but they may miss an infection when the amount of target protein is low.

    A negative rapid result therefore needs context. Symptoms, recent exposure, the disease being considered, and local clinical guidance all influence whether repeat testing or a different method is appropriate.

    Antibody tests look backward

    Serology detects antibodies produced by the immune system. It can help show that the body encountered a virus or responded to vaccination, but it generally isn't the same as detecting an active infection at the moment of testing.

    The timing of antibody development matters, and antibodies don't automatically reveal when exposure occurred or whether a person can transmit the virus. Doctors interpret serology alongside medical history and other findings.

    A test result is evidence, not a complete story. The sample, timing, method, and clinical question all shape what the result can tell you.

    The Ultimate Viral Defense, Cleaning, Wipes, and Hygiene

    Cleaning works best when you match the method to the virus and the surface. Soap removes material from hands, while a disinfectant must be used according to its label, with enough coverage and contact time to inactivate the target organism.

    Non-enveloped viruses deserve special attention. Norovirus is resistant to many common disinfectants, and public-health guidance recommends chlorine bleach or an appropriate EPA-registered product. CDC guidance uses bleach at 1,000 to 5,000 ppm, equivalent to 5 to 25 tablespoons of household bleach per gallon of water, with at least 5 minutes of contact time (norovirus disinfection guidance).

    Daily habits and outbreak cleanup aren't identical

    For ordinary daily maintenance, focus on handwashing, cleaning visibly dirty surfaces, and following the product label. During suspected norovirus contamination, use a product specifically suited to that virus. CDC-linked guidance says alcohol and disinfecting wipes alone aren't sufficient for norovirus, so don't treat every convenient wipe as interchangeable with a norovirus-effective disinfectant (public-health cleaning advice).

    For outbreak cleanup, OSHA and state guidance describe different bleach mixtures by surface:

    • Food or mouth-contact items: Use 1 tablespoon per gallon.
    • Most non-porous surfaces: Use 1/3 cup per gallon.
    • Heavily contaminated non-porous surfaces: Use 1 and 2/3 cups per gallon.
    • Contact time: Leave the solution in place for 10 to 20 minutes, then rinse where appropriate (OSHA norovirus factsheet).

    Never mix bleach with ammonia, acids, or other cleaners. Improve ventilation, wear suitable gloves, remove organic material before disinfecting, and follow the product's safety directions.

    Hands require a separate approach. Wash with soap and water, especially after using the bathroom, caring for someone who is ill, or cleaning contamination. If you handle laboratory or preparation materials, keep hygiene chemicals separate from specialised supplies such as bacteriostatic water, which has its own handling requirements.

    Your Next Steps in Virology and Staying Safe

    You don't need to memorize every virus to think like a careful beginner. Learn the structure, identify the transmission route, check the quality of the source, and choose prevention that blocks the route that actually matters.

    VirusFAQ.com offers educational and scientific articles on viral biology, transmission, prevention, and individual viruses, including Influenza, Herpes, Coronaviruses, Norovirus, HIV-1, HBV, HCV, SARS-CoV-2, and others. Pair that reading with guidance from public-health agencies and a clinician when symptoms or exposure create a medical concern.

    Misinformation makes this discipline harder to handle. A systematic review found misinformation rates ranging from 1% to 51% in vaccine-related social posts, 0.2% to 28.8% in COVID-19 posts, and 4% to 60% in pandemic-related posts; it also found that about 20% to 30% of YouTube videos about emerging infectious diseases contained inaccurate or misleading information (overview of health misinformation risks).

    Build your next habit today: learn the route of transmission for the virus you're concerned about, check the relevant public-health guidance, and stock a disinfectant whose label specifically covers that virus. Knowledge won't remove every risk, but it will help you replace panic with precise, effective action.


    Visit VirusFAQ.com to explore the virus-specific guides, then review your household cleaning products and choose one clearly labelled for the pathogens you need to manage. If you're dealing with suspected norovirus or another illness, follow public-health instructions and contact a healthcare professional for personalised advice.

  • Norovirus Symptoms vs Flu: The Definitive Guide

    Someone in the household starts vomiting without warning. A few hours later, another person develops a fever and body aches, and the family starts calling it “the flu.” That label may be wrong. Norovirus and influenza can overlap in general symptoms, but they infect different body systems, follow different timelines, and require different prevention measures.

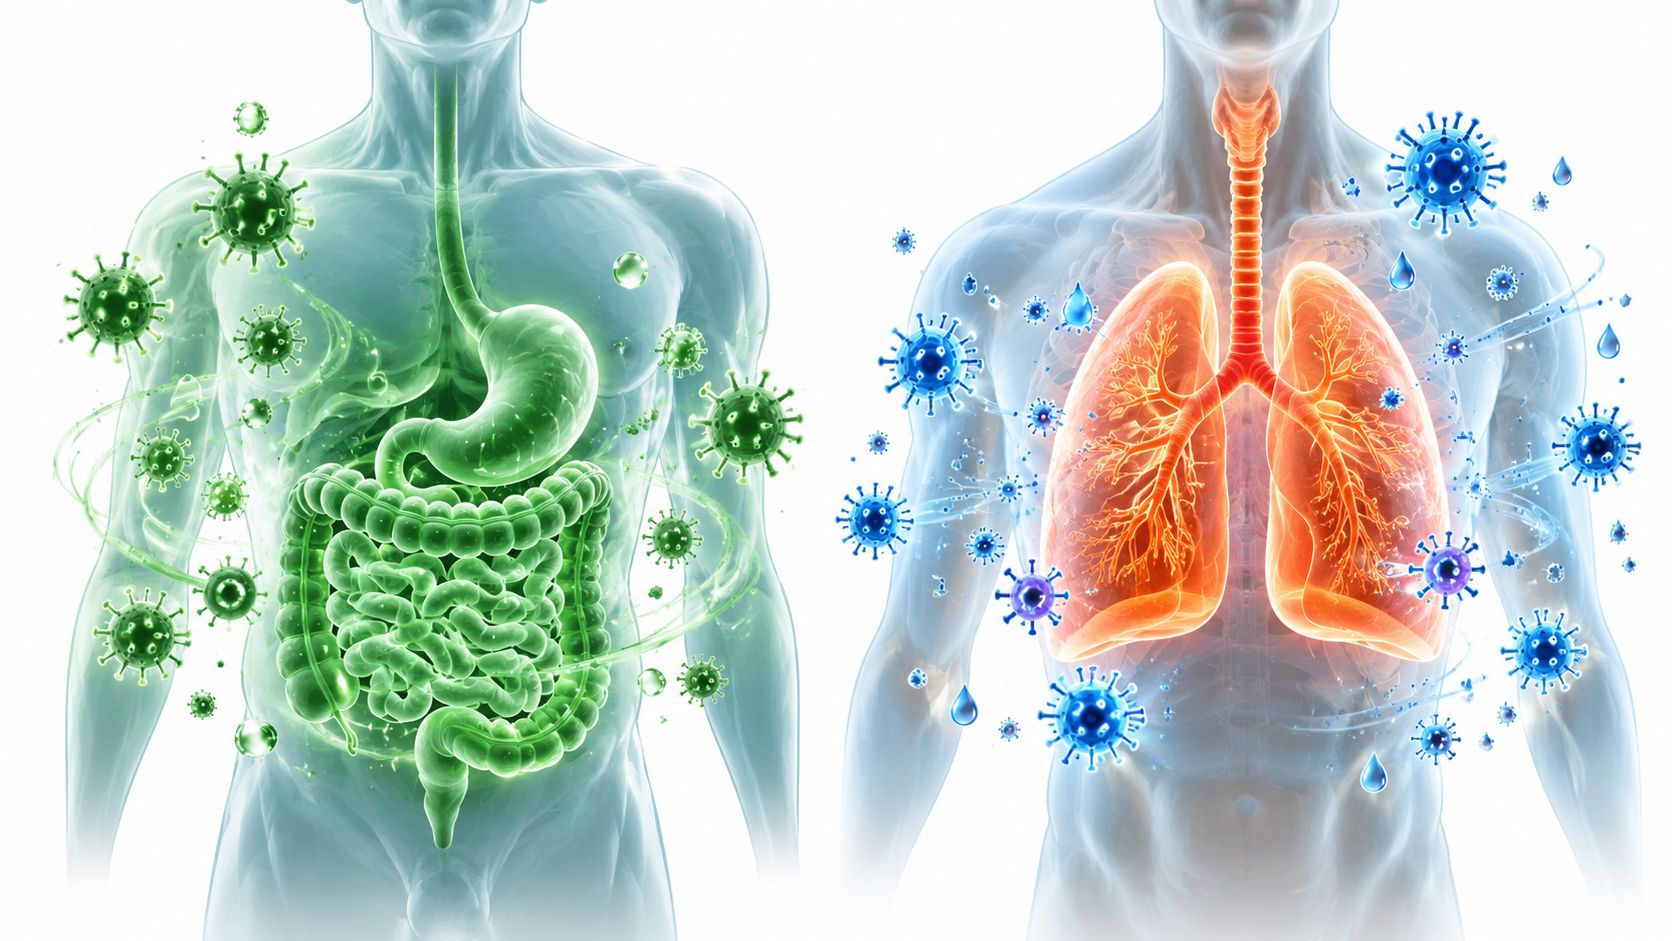
    The quickest practical distinction is the dominant symptom pattern. Sudden vomiting, watery diarrhea, nausea, and stomach pain point toward norovirus, while fever with cough, sore throat, congestion, body aches, headache, and fatigue points more strongly toward influenza. Neither pattern replaces medical evaluation, especially when symptoms are severe, but it gives you a useful starting framework.

    Understanding the Core Difference Between Norovirus and Flu

    A parent who wakes up with stomach cramps and repeated vomiting may say, “I've caught the stomach flu.” The phrase is common, but it creates a biological misunderstanding. Norovirus isn't influenza, and “stomach flu” is only a nickname for a gastrointestinal illness.

    Norovirus primarily affects the stomach and intestines. It typically causes sudden vomiting, watery diarrhea, nausea, and stomach pain. Symptoms usually begin 12 to 48 hours after exposure and last about 1 to 3 days, according to the Centers for Disease Control and Prevention's overview of norovirus symptoms.

    Influenza affects the respiratory system, including the nose, throat, and lungs. Flu commonly produces fever, cough, sore throat, a runny or stuffy nose, muscle or body aches, headache, and fatigue. Vomiting or diarrhea can occur with influenza, particularly in children, but digestive symptoms aren't usually the central presentation in adults.

    An infographic comparing the symptoms of Norovirus stomach flu to influenza respiratory illness with illustrated icons.

    Why the nickname causes confusion

    The confusion comes from symptoms that both infections can produce. Fever, headache, fatigue, and body aches can occur with either illness, so someone with norovirus may feel generally sick in a way that resembles influenza. A child with influenza may also vomit, making the distinction less obvious.

    The body system taking the greatest hit is more informative than the presence of one isolated symptom. If the illness centers on the digestive tract, norovirus becomes more likely. If cough, sore throat, nasal congestion, and breathing-related discomfort dominate, influenza becomes more likely.

    The distinction also affects public-health behavior. Norovirus requires careful attention to bathroom hygiene, contaminated surfaces, food preparation, and cleanup after vomiting. Influenza prevention focuses more heavily on respiratory exposure, ventilation, staying away from symptomatic people, and vaccination.

    The CDC's Yellow Book discussion of norovirus describes norovirus as the most common cause of viral gastroenteritis and estimates that it causes about 19 to 21 million illnesses each year in the United States. The same source estimates that norovirus is responsible for roughly 50% of foodborne disease outbreaks. Those figures help explain why a short gastrointestinal illness can still create a substantial community burden.

    Practical rule: “Stomach flu” describes a symptom location, not a relationship between norovirus and influenza.

    Comparing Symptoms and Clinical Presentation

    A useful way to compare norovirus symptoms vs flu is to ask one question first: Which symptom appeared early and became most disruptive? Sudden, repeated vomiting or watery diarrhea points toward norovirus. Cough, sore throat, chills, and respiratory congestion point toward influenza.

    Feature Norovirus Influenza
    Main body system Stomach and intestines Nose, throat, and lungs
    Typical dominant symptoms Vomiting, watery diarrhea, nausea, stomach pain Fever, cough, sore throat, congestion, body aches, headache, fatigue
    Digestive symptoms Central to the illness Can occur, especially in children
    Onset after exposure 12 to 48 hours About 1 to 4 days
    Most useful clue Gastrointestinal distress Respiratory illness with systemic symptoms

    Norovirus often begins with a sharp change from normal health to intense gastrointestinal distress. A person may feel fine earlier in the day, then develop nausea, vomiting, cramps, and diarrhea in quick succession. Fever, headache, or body aches may appear, but they usually accompany the digestive illness rather than define it.

    Influenza can also begin abruptly, but its pattern is different. Fever, chills, cough, sore throat, headache, fatigue, and body aches form the more recognizable clinical picture. Vomiting or diarrhea doesn't rule out flu, particularly in children, yet prominent gastrointestinal symptoms without cough or sore throat are less typical of influenza.

    A comparison chart outlining the differences in onset, severity, symptoms, fever, duration, and treatment between cold and flu.

    How overlap leads to mistakes

    One shared symptom can pull attention away from the overall pattern. For example, a person with norovirus may have body aches and a headache from fluid loss and systemic illness. A child with influenza may vomit, causing caregivers to assume that a stomach virus is responsible.

    The timing adds another clue. Norovirus symptoms usually start 12 to 48 hours after exposure, while influenza symptoms usually begin about 1 to 4 days after exposure, as described by the Mayo Clinic's norovirus symptom guidance. Both illnesses can appear suddenly, but norovirus usually has the shorter interval between exposure and symptoms.

    For broader context on how common viral illnesses differ, see this overview of common virus infections. It can help place norovirus and influenza within the wider group of infections that cause respiratory, gastrointestinal, or systemic symptoms.

    Onset, Incubation, and Typical Duration

    The clock matters because the time between exposure and symptoms can support, but never independently prove, a diagnosis. Norovirus usually has an incubation period of 12 to 48 hours, meaning symptoms often arrive soon after contact with a contaminated person, surface, food, or environment. Influenza generally takes about 1 to 4 days to produce symptoms after exposure.

    Consider two situations. A person develops abrupt vomiting the day after a shared meal or after caring for someone with diarrhea. That timing fits norovirus. Another person develops fever, cough, sore throat, and aches several days after close contact with someone who had a respiratory illness. That sequence fits influenza more closely.

    A desk calendar, an analog clock, and a glass of water on a white surface.

    Short illness does not mean minor illness

    Norovirus is often intense but brief. Acute symptoms typically last about 1 to 3 days, although dehydration can make the illness dangerous, particularly for young children, older adults, and people with weakened immune systems. The speed of onset can make norovirus feel more dramatic than its duration might suggest.

    Influenza often has a more extended recovery pattern. The initial fever and respiratory symptoms may improve, while cough or fatigue continues to affect daily activities. The precise course varies by the individual, age, underlying health, and complications, so a longer illness doesn't automatically confirm flu.

    A timeline can clarify what happened:

    1. Exposure: Record likely contact with illness, shared food, contaminated surfaces, or respiratory droplets.
    2. First symptom: Note whether vomiting and diarrhea or cough and sore throat appeared first.
    3. Progression: Watch whether digestive or respiratory symptoms remain dominant.
    4. Recovery: Track hydration, fever, breathing, and the ability to resume normal activity.

    A short illness still deserves attention if the person can't replace lost fluids or develops worsening symptoms. For a focused discussion of the gastrointestinal illness timeline, consult this guide to how long norovirus lasts.

    Transmission Routes and Contagiousness

    Norovirus and influenza spread through different pathways, so cleaning and distancing decisions should match the suspected virus. Norovirus commonly spreads through the fecal-oral route, including direct contact, contaminated food or water, and surfaces touched after bathroom use. Vomiting can also release infectious material into the surrounding environment, allowing contamination beyond the person who is sick.

    That pathway explains why norovirus outbreaks move quickly through households, schools, healthcare settings, food-service environments, and shared accommodation. A contaminated bathroom handle, faucet, toilet surface, towel, or countertop can become part of the transmission chain. A person may also spread the virus while preparing food for someone else.

    Norovirus is a non-enveloped virus, a structural feature associated with greater environmental stability than many enveloped viruses. That doesn't mean every surface remains infectious indefinitely, but it does mean ordinary cleaning habits may not be enough after vomiting or diarrhea.

    Influenza is primarily a respiratory infection. An infected person can release respiratory particles while coughing, sneezing, talking, or breathing near others. Those particles can reach another person's respiratory tract, especially during close contact or in poorly ventilated spaces.

    Containment requires different habits

    For suspected norovirus, isolate the sick person from food preparation and focus on bathroom and surface hygiene. Clean visible contamination promptly, use appropriate disinfectant products, and wash hands with soap and water. Hand sanitizer alone shouldn't be treated as a substitute for handwashing in a norovirus situation.

    For suspected influenza, reduce close respiratory contact, improve airflow, cover coughs and sneezes, and avoid sharing personal items. Respiratory precautions won't address contaminated vomit or fecal material, just as wiping a countertop won't replace measures that reduce inhalation exposure.

    The norovirus transmission guide from VirusFAQ provides additional context on fecal-oral spread, contaminated objects, and exposure during vomiting. Understanding the route helps you choose the right intervention instead of applying one generic “disinfect and isolate” plan to every virus.

    Diagnostic Approaches and Medical Treatment

    Doctors often begin with the symptom pattern, exposure history, and local outbreak context. Norovirus may be diagnosed clinically when sudden vomiting and diarrhea affect several people in the same setting. Specialized stool testing can confirm norovirus, but testing isn't always necessary for an uncomplicated illness.

    Influenza may also be recognized from its characteristic respiratory presentation, particularly during periods of widespread flu activity. Rapid molecular tests and other clinical assays can help confirm influenza when the result would affect treatment or infection-control decisions.

    Neither infection responds to antibiotics. Antibiotics target bacteria, while norovirus and influenza are viruses. Taking an antibiotic without an appropriate bacterial diagnosis can expose someone to side effects without treating the cause.

    Supporting recovery from norovirus

    Norovirus treatment centers on replacing lost water and salts. Take small, frequent sips if large drinks trigger more vomiting. Oral rehydration fluids can be useful because they provide both fluid and electrolytes. A person who can't keep fluids down, becomes unusually weak or confused, or shows signs of dehydration needs medical advice.

    There isn't a specific antiviral treatment routinely used to clear norovirus. Rest, careful fluid replacement, and monitoring are the central measures for patients in general.

    Managing influenza

    Flu care may include rest, fluids, and symptom relief. A clinician may prescribe antiviral medication, particularly when treatment begins early or when the patient has factors that increase the risk of complications. Medical advice is especially important for people with serious underlying conditions, very young children, older adults, and those with weakened immune systems.

    Norovirus also changes return-to-work and school decisions. The CDC advises staying home for 48 hours after symptoms stop, and people should avoid preparing food for others during that period. Feeling better isn't the same as no longer posing a transmission risk.

    Prevention Strategies and When to Seek Care

    Norovirus prevention starts with soap-and-water handwashing, especially after using the toilet, helping someone who is sick, cleaning vomit or diarrhea, and before preparing food. Alcohol-based hand sanitizer shouldn't replace this step because it isn't reliable against norovirus.

    Surface cleaning needs equal attention. After vomiting or diarrhea, wear disposable gloves when possible, remove visible contamination carefully, and use a bleach-based disinfectant suitable for the surface. Follow the product label, maintain ventilation, and never mix bleach with other cleaners. Wash contaminated clothing, towels, and bedding separately when practical.

    Influenza prevention has a different center of gravity. Annual vaccination, respiratory etiquette, staying home while ill, reducing close contact, and improving indoor airflow all help limit respiratory spread. Hand hygiene still matters, but it can't replace measures that reduce inhalation of infectious respiratory particles.

    An infographic showing prevention strategies for illness and specific symptoms that require seeking medical care.

    Warning signs that need medical attention

    Seek prompt medical care for severe or worsening symptoms, especially:

    • Dehydration: Dry mouth, dizziness, unusual weakness, or inability to replace fluids can signal a serious problem.
    • Breathing difficulty: Shortness of breath, chest discomfort, or labored breathing requires urgent evaluation.
    • Blood: Blood in vomit or stool isn't a routine feature to manage at home.
    • Persistent fever: A high or ongoing fever deserves professional assessment, particularly when combined with confusion or marked fatigue.
    • Inability to drink: Repeated vomiting that prevents fluid intake creates a rapid dehydration risk.

    Norovirus is often short-lived, but its contagiousness continues after symptoms improve. Stay home for 48 hours after symptoms stop, avoid food preparation during that period, and clean frequently touched surfaces. Families caring for infants can also use this practical guide to newborn hygiene routines when building consistent handwashing, changing, and household-cleaning habits.

    The symptom distinction is straightforward: vomiting, diarrhea, and stomach pain are more consistent with norovirus, while fever, chills, cough, headache, and other respiratory symptoms are classic for influenza, as summarized by the Cleveland Clinic's influenza symptom guide. When symptoms don't fit either pattern, become severe, or affect someone medically vulnerable, contact a healthcare professional rather than relying on labels.


    If vomiting, diarrhea, cough, or fever is affecting your household now, write down the first symptom, likely exposure, fluid intake, and any warning signs. Use that record when contacting a clinician, stay home while contagious, and follow VirusFAQ.com for practical, evidence-based guidance on virus transmission, prevention, and household hygiene.

  • Environmental House Cleaning: Stopping Viral Spread Safely

    Norovirus requires only about 18 viral particles to cause infection, which is why environmental house cleaning matters even when a surface looks spotless. Stopping spread depends on removing contamination and using the right disinfectant for the right wet contact time.

    A household outbreak rarely announces itself with visible dirt. Someone becomes ill, touches a bathroom handle, opens a refrigerator, or picks up a remote, and another person later touches the same object before touching their face or eating. That ordinary sequence is fomite transmission, the movement of infectious material from a surface to hands and then to the mouth, nose, or eyes.

    Environmental house cleaning is therefore more than an aesthetic routine. It combines surface cleaning, targeted disinfection, air management, and fabric care to interrupt transmission without creating unnecessary chemical exposure. The most effective approach isn't automatically the harshest product or the label with the most reassuring environmental language. It is the method that matches the hazard.

    Why Environmental House Cleaning Matters for Virus Prevention

    A clean-looking surface can still carry risk

    Visible grime and infection risk overlap, but they aren't the same thing. A polished faucet may still become a route for transmission after an ill person uses it, while a dusty corner may be unpleasant without being the immediate source of an outbreak.

    Norovirus illustrates the problem sharply. The infectious dose is about 18 viral particles, according to the CDC's norovirus prevention guidance. A small amount of contamination can therefore matter, especially in shared bathrooms, kitchens, childcare settings, and homes where several people use the same touchpoints.

    Consider a typical evening. One family member vomits or has diarrhea, washes their hands, and steadies themselves on the bathroom door handle. Another person opens that door, checks a phone, and prepares food. The virus doesn't need to spread across every surface in the home. It only needs a few connected opportunities to move from a contaminated object to a hand and then to the face or food.

    Practical rule: Clean the objects people touch repeatedly, not just the surfaces that look dirty.

    Cleaning interrupts a chain

    The chain usually includes a source, a surface, a hand, and a vulnerable entry point. Environmental house cleaning weakens that chain in several ways:

    • Remove soil first. Detergent and water lift organic material and debris that can shield contamination.
    • Disinfect selectively. A suitable product can inactivate pathogens on compatible hard surfaces when its label conditions are followed.
    • Reduce transfer. Damp cloths, disposable materials where appropriate, and handwashing limit movement between rooms.
    • Control recontamination. A disinfected handle can become contaminated again if the source remains ill or cleaning tools are reused carelessly.

    Viruses differ in their resistance and behavior. Non-enveloped viruses such as norovirus and rotavirus demand particular care because a quick wipe may not provide the exposure needed for reliable inactivation. A household doesn't need to panic or sterilize every possession. It does need a deliberate response in high-risk areas after vomiting, diarrhea, or another known contamination event.

    The practical standard is simple: treat environmental house cleaning as a public-health barrier, while keeping the response proportionate. Remove contamination promptly, disinfect where transmission is plausible, and avoid spreading particles through dry cleaning methods.

    The Science Behind Effective Disinfection

    Cleaning and disinfection do different jobs

    Cleaning removes soil. Disinfection acts on microorganisms that remain after or during the cleaning process. Combining those steps casually can leave a surface visually improved but microbiologically inadequately treated.

    A controlled household study found that detergent with hot water produced no observable reduction in microbial contamination, while hypochlorite and phenolic disinfectants produced substantial bacterial reductions. The same household disinfectant study also found that the benefit was short-lived, with contamination only marginally below baseline again after about 3 to 6 hours.

    That finding doesn't make detergent useless. It shows that detergent cleaning and residual disinfection aren't interchangeable. Cleaning removes the material that can interfere with a disinfectant, while disinfection requires a product and process capable of acting on the target organism.

    An infographic detailing the five-step scientific process of effective surface disinfection to promote healthier environments.

    Wet contact time is the hidden variable

    Disinfectants need time in contact with a wet surface. If a product is sprayed and immediately wiped away, the surface may never receive the labeled exposure.

    Think of contact time like allowing a stain remover to sit before scrubbing. The liquid must remain present long enough for its chemistry to work. Product labels control this detail, so use the stated wet time rather than assuming that a fast pass is sufficient.

    The EPA disinfectant-wipe label shows that some products specify a 1-minute wet contact time. Its efficacy language for tough, non-enveloped viruses includes feline calicivirus, norovirus, rhinovirus, and rotavirus as test organisms used to support claims. That doesn't mean every wipe works against every virus. It means the user must check the exact label, target organism, surface compatibility, and required wet time.

    WHO surface-disinfection guidance recommends a minimum contact time of 1 minute for coronavirus disinfection unless the manufacturer specifies otherwise. The broader lesson applies across products: don't confuse speed with efficacy.

    Green chemistry still requires technical discipline

    The modern environmental cleaning movement grew from late twentieth-century concern about chemical exposure and environmental damage. The history of green cleaning describes the influence of environmental concern in the 1960s and 1970s, phosphate restrictions in the 1980s and 1990s, and later emphasis on life-cycle assessment, eco-labels, and circular-economy thinking.

    That history matters because safer formulation and effective disinfection aren't opposing goals. The correct question is whether a product is appropriate for the pathogen and used according to its label. “Natural” doesn't replace concentration, coverage, or contact time.

    Green Cleaning Myths and Indoor Air Quality Risks

    Eco-labels do not answer the air-quality question

    The global market for eco-friendly cleaning products is estimated at USD 13.2 billion in 2025, rising to USD 14.3 billion in 2026 and projected to reach USD 33.6 billion by 2035, with a long-run CAGR of 10%, according to this market overview of eco-friendly cleaning products.

    That growth reflects rising demand for biodegradable, lower-toxicity, and sustainability-labeled products. It does not show that every product improves indoor air chemistry. An eco-label may address ingredients, packaging, or environmental impact while saying little about what the formula releases during use.

    A 2024 study found no strong evidence that green cleaners improve indoor air quality compared with regular products. Fragranced products marketed as green can emit monoterpenes. Indoors, those compounds may react with oxidants and form secondary pollutants, including formaldehyde and PAN species. Fragrance-free products produced far fewer VOCs in the same research, as reported in the study of emissions from fragranced and fragrance-free cleaners.

    Choose the exposure profile, not the marketing adjective

    For routine cleaning, use a short decision process:

    • Fragrance-free formulas: Fewer added scent compounds generally mean fewer fragrance-related emissions.
    • Low-VOC labeling: Treat this as an exposure consideration, not proof that a product disinfects.
    • Ventilation: Open suitable windows or run exhaust ventilation while cleaning and afterward.
    • Task-specific products: Reserve disinfectants for situations where pathogen risk justifies their use instead of applying them across every surface.

    Method matters as much as formulation. Damp wiping captures soil and particles, while dry dusting can redistribute them into the breathing zone. Apply enough solution to clean effectively, avoid unnecessary spraying, and allow ventilation to clear vapors. During painting or renovation, related choices also affect exposure. The resource on indoor air quality and painting offers practical advice for considering those sources together.

    A biodegradable cleaner can still release irritating compounds indoors. A disinfectant may also be appropriate during a high-risk contamination event, even if it has a greater environmental burden than a routine dusting product. Environmental house cleaning should assess three separate factors: environmental burden, indoor air exposure, and microbial efficacy.

    For virus-specific surface decisions, VirusFAQ.com provides guidance on cleaning and disinfecting. Choose the least-emitting product that meets the hygiene requirement, use it with the correct damp method, and ventilate instead of treating scent as evidence of cleanliness.

    High-Risk Areas and Targeted Cleaning Protocols

    Start with the contamination event

    Vomiting or diarrhea requires prompt cleaning and disinfection of contaminated hard surfaces. Norovirus cleanup calls for a chlorine bleach solution of 1,000 to 5,000 ppm, equivalent to about 5 to 25 tablespoons of household bleach per gallon of water, with at least 5 minutes of wet contact time, according to EPA norovirus cleanup guidance.

    Use a controlled sequence:

    1. Put on disposable gloves and improve ventilation if possible.
    2. Cover and remove visible contamination with disposable absorbent material.
    3. Clean the area, then apply the bleach solution or an EPA-registered disinfectant effective against norovirus.
    4. Keep the surface visibly wet for the full 5 minutes.
    5. Clean again with soap and hot water where specified, then wash hands thoroughly.

    Never mix bleach with ammonia, acids, or other cleaners. Check product directions, confirm surface compatibility, and discard or launder cleaning materials safely. Fragrance-free products are preferable where possible because a strong scent does not prove that a surface is disinfected.

    Use a room-by-room target list

    Bathrooms need prompt attention because illness can contaminate nearby fixtures and floors. In kitchens, clean handles, faucets, counters, refrigerator pulls, and surfaces touched during food preparation. Across the home, include doorknobs, light switches, toilet flush handles, phones, keyboards, and remotes used by an ill person.

    Situation First action Disinfection choice
    Routine soil without known illness Clean with detergent and water Disinfect only when risk warrants it
    Known norovirus contamination Remove soil promptly Bleach at the specified range or an EPA-registered norovirus product
    Small high-touch area Clean if visibly soiled A labeled disinfecting wipe can be practical
    Sensitive material Check compatibility first Use only a product approved for that surface

    Wipes can limit dosing errors, but their label still controls the decision. Check the listed organism, approved surface, and wet contact time. Some products specify 1 minute, while a wipe that dries sooner may not meet its claim.

    Surface note: Dirty window tracks can hold dust and organic debris. Understanding why dirty window tracks matter helps residents include these overlooked areas in routine cleaning, although they do not replace outbreak-focused disinfection of high-touch surfaces.

    Fomite transmission is the transfer of pathogens through contaminated objects and surfaces. Clear guidance on how fomite transmission works helps households prioritize surfaces connected to the contamination event instead of treating every object as equally hazardous. Use damp cleaning methods to capture soil, and avoid dry dusting that can redistribute contaminated particles into the air.

    Ventilation and Laundry Strategies for Reduction

    The cleaning method changes what enters the air

    Dry dusting and dry mopping can push dust and allergens back into circulation. That matters in homes with asthma, allergies, mold concerns, or wildfire smoke residue, where the cleaning process itself can increase short-term exposure.

    Use a damp microfiber cloth on hard surfaces, working from cleaner areas toward dirtier ones. For floors and carpets, a HEPA vacuum can capture fine particles more effectively than a dry broom. Avoid shaking cloths, rugs, or bedding indoors, and bag heavily contaminated disposable materials before taking them out.

    A residential monitoring study found post-cleaning concentration increases in about 60% of measured VOCs and about 80% of measured SVOCs. Most peaks faded within a few hours, but some lower-volatility compounds persisted for more than 5 hours, and carpet spot cleaning produced 2-butoxyethanol emissions that remained high for days, according to the study of residential cleaning emissions.

    A house illustration showing energy-efficient ventilation, a washing machine, and clothes drying on a rack.

    Treat air, surfaces, and textiles as one system

    Run bathroom and kitchen exhaust fans so moisture and airborne contaminants leave the home rather than spreading through it. Guidance from the New York State Department of Health on healthy homes also emphasizes damp cleaning, HEPA vacuuming, ventilation, MERV 13 filtration, and HEPA air cleaners as parts of a broader indoor-air strategy.

    Laundry can undo careful surface work if contaminated textiles are handled casually. Keep soiled clothing, towels, and bedding contained, avoid snapping or shaking them, wash them with detergent using the warmest suitable cycle, and dry them completely according to the fabric care instructions. Clean hands and the laundry area after handling items from an ill person.

    For a wider framework covering household air management, see this resource on indoor air quality improvement. Ventilation won't replace disinfection, and a purifier won't remove contamination from a handle. Each control addresses a different route of exposure.

    Creating a Sustainable Cleaning Schedule

    Match effort to risk

    A sustainable schedule distinguishes ordinary maintenance from an active illness response. Routine cleaning can focus on soil, moisture, dust, and frequently touched surfaces. Outbreak cleaning requires faster action, a suitable disinfectant, correct wet time, and attention to items used by the ill person.

    A practical weekly pattern might look like this:

    • High-touch check: Clean handles, switches, faucets, remotes, and appliance pulls according to household use.
    • Damp maintenance: Wipe surfaces and mop with a damp method rather than redistributing dry dust.
    • Air and fabric care: Vent moisture-prone rooms, maintain filtration, vacuum with HEPA equipment, and launder shared textiles.
    • Illness response: After vomiting or diarrhea, isolate the task, remove soil, disinfect affected hard surfaces, and follow the product's label.

    Prefer repeatable routines over panic cleaning

    Damp microfiber cleaning is generally the better default for dust and allergen control, while disinfecting wipes are useful for small, compatible, high-touch surfaces when their label supports the intended pathogen and contact time. Bleach has an important role in norovirus cleanup, but using it for every routine task can increase odor and chemical exposure without adding proportional protection.

    Don't let an eco-label make the decision by itself. Ask three questions: What am I trying to remove? Which pathogen, if any, is relevant? How long must the surface stay wet? That short checklist prevents both under-treatment and unnecessary product use.

    The strongest environmental house cleaning plan is consistent, targeted, and comfortable enough to maintain. Keep fragrance-free, low-VOC routine products available, reserve stronger disinfectants for defined risks, use damp tools, ventilate during and after cleaning, and teach every household member why contact time matters.


    If your neighborhood association is preparing shared cleaning guidance, create a written protocol for bathrooms, kitchens, high-touch surfaces, laundry, and ventilation. Share the product labels, dilution instructions, and wet contact times with residents so that the next illness response is calm, coordinated, and effective.

  • C Fold vs Multifold Paper Towels: Which Works Better?

    You're standing outside a busy clinic washroom when the dispenser starts behaving strangely. A patient pulls the handle, several towels come out together, and the next user finds a loose pile on the floor. The maintenance worker has loaded the wrong folded format, and a small refill mistake has become a queue, a mess, and a hygiene complaint.

    That's the practical issue behind C fold vs multifold. The folds aren't cosmetic. They determine how sheets sit in the dispenser, how many come out per pull, how often staff refill the unit, and how much contact users have with the remaining stock. C-fold towels are older, flat-stacked sheets widely used in commercial settings, while multifold towels interlock to help present one sheet at a time. Industry guidance on C-fold format and dispensing and commercial fold comparisons both point to the same operational distinction.

    Decision factor C fold Multifold
    Basic structure C-shaped sheet, stacked flat Interfolded or zigzag sheet
    Sheet presentation Flat stack, manual separation Next towel presents automatically
    Main advantage Familiar format for compatible dispensers Better portion control
    Main risk Multiple sheets can pull together Poor performance in an incompatible dispenser
    Best fit Existing C-fold hardware and simple public washrooms Compatible enclosed dispensers and hygiene-focused areas

    Why the Fold You Pick Actually Matters

    A folded towel dispenser is a small mechanical system. The stack has to remain aligned, the opening has to release the leading sheet, and the next towel has to move into position without tearing. Change the fold, and you change each of those conditions.

    Three operational effects to watch

    Clump pulling is the first failure. C-fold towels aren't interlocked, so a user may grip the exposed edge and pull several sheets from the stack. The towels can bunch at the opening, fall forward, or land partly outside the cabinet. Guidance from The Cleaning Station describes the structural difference directly: C-fold sheets lie stacked, while multifold sheets overlap to support one-at-a-time dispensing.

    The second effect is user compensation. When people receive a damp or crumpled sheet, they often reach back for another. That response isn't caused only by absorbency. It can begin with poor presentation, a torn edge, or a dispenser opening that makes the first sheet difficult to grasp.

    The third effect appears on the cleaning schedule. A dispenser that releases multiple sheets empties faster, especially during busy periods. Staff then make additional refill visits, while discarded towels increase the pressure on waste bins and the floor around the unit.

    Practical rule: Treat the towel and dispenser as one operating system. A format that performs well in its intended hardware can fail when loaded into the wrong cabinet.

    The decision therefore isn't merely whether multifold is “better.” It's whether the current dispenser, traffic pattern, refill routine, and hygiene requirements support the format you're buying. In a school corridor, a durable existing C-fold unit may be more practical than an immediate hardware replacement. In a clinic, controlled presentation and enclosed storage may justify multifold equipment.

    The rest of the decision comes down to three trade-offs: geometry, which controls dispensing; consumption, which affects waste and labor; and hygiene, which depends on how users and staff interact with the unit.

    What Each Fold Actually Looks Like

    A C-fold towel has two folds that create a C shape, then sits in a flat stack. The sheet is often a larger format, around 30 x 23 cm before folding, as shown in Foremost's comparison of hand-towel folds. Each towel remains separate, so the user pulls directly from the stack. The dispenser does not present a connected successor.

    A multifold towel, also called an M-fold in some product descriptions, uses an interfolded or layered arrangement. One sheet overlaps the next, helping position it at the opening after removal. These towels are often smaller in footprint, around 24–27 x 23 cm, so the fold carries more of the portion-control work.

    A visual guide displaying ten different white napkin folding techniques on dinner plates with their names.

    Why the shape changes the user experience

    The practical difference appears at the dispenser opening. A C-fold stack resembles separate cards. A careful pull may remove one towel, but an angled grip, loose stack, or narrow opening can bring several sheets forward. In a busy school or office washroom, that turns a fold choice into a consumption and refill issue.

    A multifold stack behaves more like a connected chain. Each towel helps position the next one, which is why Tork's explanation of C-fold and Z-fold towels associates interleaved presentation with fewer multiple-sheet touches. The result depends on the cabinet, not the fold alone. Opening width, stack height, loading direction, and towel dimensions all affect feeding.

    A partly empty dispenser can expose the same weakness differently. C-fold towels may shift or spread inside the cabinet, while multifold towels may stop feeding if their dimensions do not match the guide.

    The useful distinction

    C-fold is stacked and independent. Multifold is overlapped and sequential. That structural difference affects how the first towel is gripped, how the next towel appears, and how reliably the stack feeds during active use.

    C Fold vs Multifold at a Glance

    The table below is a buying reference, but it shouldn't replace a dispenser check. Manufacturers use different sheet sizes and pack configurations, so the exact product specification still controls compatibility.

    Attribute C Fold Multifold
    Fold pattern C-shaped fold Interfolded, zigzag, or layered fold
    Sheet arrangement Flat stack Overlapping stack
    Typical unfolded format Often around 30 x 23 cm before folding Usually around 24–27 x 23 cm
    Approximate length examples C-fold sheets are typically about 32 cm long M-fold sheets are typically about 32 cm long
    Presentation Leading sheet is pulled from a stack Next sheet partially presents after removal
    Dispensing behavior May release several towels at once Designed for one-at-a-time dispensing
    Footprint Generally larger Usually smaller
    User grip Pulls a flat, folded edge Grasps a presented leading edge
    Common hardware relationship Older or universal folded-towel dispensers Compatible single-sheet-release dispensers
    Main operational concern Over-pulling and loose stacks Jams or poor feeding if the dispenser isn't compatible

    The most important contrast isn't the number of panels. It's the relationship between the sheet and the opening. C-fold towels depend more heavily on the user pulling neatly from a stable stack. Multifold towels use the overlap between sheets to guide presentation.

    That difference also affects how a buyer should compare products. A larger C-fold sheet may feel generous in the hand, but a larger sheet doesn't automatically mean lower consumption. If the dispenser releases multiple towels or users take an extra sheet because the first one is awkward, the nominal sheet size tells only part of the story.

    Likewise, a multifold towel's smaller footprint isn't evidence that it will always dry hands less effectively. Commercial towel guides describe multifold towels as often slightly more absorbent and capable of drying hands with fewer sheets, but performance still depends on the paper construction and how users dispense it. The Cleaning Station's folded-towel guide also emphasizes that cost per use depends on actual consumption, not just the case price.

    Use this table as a checklist. Confirm the opened dimensions, folded dimensions, ply, pack count, and dispenser specification before treating one format as a drop-in substitute for the other.

    Dispenser Compatibility and the Switch Question

    The most common purchasing error is assuming that “universal” means every folded towel will feed equally well. It doesn't. Some standard dispensers accept both formats, but multifold towels perform best in hardware designed for single-sheet release, while C-fold towels need enough tray space and a suitable opening for a flat stack.

    An open-face or recessed folded-towel cabinet may accommodate C-fold stock. The stack sits flat, and the user pulls the exposed fold. As the stack becomes low, the remaining towels can lose support and fall forward, which makes presentation less consistent.

    Multifold towels generally suit enclosed dispensers with an opening, valve, or push-bar arrangement that supports sequential feeding. The key is not the brand label alone. Check the dispenser's accepted fold, opening dimensions, maximum stack height, and loading direction. A folded-towel dispenser compatibility guide also highlights the practical gap between theoretical compatibility and reliable real-world dispensing.

    What goes wrong during an emergency swap

    Loading C-fold towels into a multifold dispenser can create a compressed or bunched stack. The leading sheet may fail to present, tear at the opening, or force the user to pull repeatedly. That encourages handfuls of towels and leaves crumpled sheets around the unit.

    The reverse problem is less dramatic but still wasteful. Multifold towels placed in a C-fold tray may slump inside the cabinet, sit below the intended pickup point, or release more than one sheet because the tray doesn't support the interfolded stack correctly.

    Don't rely on a verbal product description during a refill emergency. Measure the dispenser opening and interior clearance, then compare those measurements with the supplier's unfolded and folded dimensions. Confirm whether the unit is rated for C-fold, multifold, or both.

    Dispenser type Compatible fold Incompatible fold Failure mode
    Open-face flat tray C fold, where specified Multifold if the tray doesn't support it Slumping or multiple-sheet pulls
    Enclosed folded-towel cabinet C fold or multifold, depending on model Any unapproved format Jams, tearing, or poor presentation
    Single-sheet-release dispenser Multifold Loose C-fold stack Leading sheet fails to feed cleanly
    Universal folded-towel dispenser Check manufacturer specification Unverified format Unpredictable dispensing
    Recessed legacy cabinet Usually C fold Multifold without fit confirmation Stack instability or blocked opening

    Product families such as Tork H1 and H2 equivalents illustrate why model identification matters, while Kimberly-Clark formats also vary by dispenser system. Don't order by a general “folded towel” description. Match the towel SKU to the mounted dispenser documentation, especially when replacing stock from another manufacturer.

    For a deeper hardware checklist, review this guide to folding paper towel dispensers. A switch can work, but it should be treated as a controlled compatibility test, not an automatic upgrade.

    Absorption, Drying, and Sheets Per Use

    A school washroom can show the difference quickly. One visitor pulls a single towel, another takes several after a weak first release, and the next person faces a depleted or untidy stack. Both C-fold and multifold towels can dry hands effectively, but their format influences portion control, handling, and replenishment work.

    C-fold towels often provide a larger individual sheet. That surface area can support effective drying, yet the benefit declines when the dispenser releases multiple towels or users take another sheet because the first pull feels inadequate. A larger sheet therefore does not automatically mean lower consumption.

    Multifold towels present a defined portion through their interlocked design. The next towel appears at the opening as one sheet is removed, so users can usually begin drying without reaching into the stack. Tork's guidance on dispensing mechanisms connects controlled dispensing with reduced handling and improved hygiene conditions. In active washrooms, that distinction also makes unusual consumption easier for facilities staff to spot.

    An infographic showing paper towel benefits including 6x absorption, 2x faster drying, and 1 sheet per use efficiency.

    The hygiene connection

    Dispensing affects hygiene through user contact. A jammed opening invites repeated tugging, while a stack that releases several towels may lead users to touch adjacent sheets before discarding the excess. Interleaved formats can reduce that interaction, provided the dispenser feeds them correctly. A poorly fitted unit can reverse the intended benefit through jams and repeated handling.

    The towel itself is not a disinfectant. Surface disinfection depends on wipe chemistry and wet contact time. The PREempt wipe reference sheet specifies a 3-minute wet contact time for hard, non-porous surfaces, which applies when staff clean dispenser levers, cabinet fronts, and nearby touchpoints.

    A controlled study found that disinfectant wipes with active ingredients achieved about 5.5 to 6.6 log10 inactivation under tested conditions, while a plain cloth transferred about 4 log10 to another carrier. The Frontiers in Public Health study shows why cleaning product and method matter alongside towel format.

    Cost and Waste Implications

    A facilities manager shouldn't compare C-fold and multifold by carton price alone. The meaningful unit is the cost per completed hand dry, which includes the number of towels dispensed, premature refills, jam clearing, and waste handling.

    Verified guidance indicates that C-fold towels may require about three to four times as many per use as M-fold towels in some operating contexts, although actual consumption depends on the dispenser, towel quality, and user behavior. The folded-paper-towel comparison presents that industry claim alongside the dimensional differences between formats.

    That range shouldn't be converted into a universal budget promise. A well-maintained C-fold dispenser may perform better than an overloaded or damaged unit, while a poorly matched multifold dispenser can erase the intended advantage through jams and failed presentation.

    What to measure before approving a change

    Track the variables that your purchasing file usually misses:

    • Sheets removed: Compare case depletion with restroom visits or another consistent usage measure.
    • Refill events: Record when staff refill early, especially during known busy periods.
    • Discarded towels: Look for floor waste, crumpled piles, and towels left beside bins.
    • Service time: Log jam clearing and extra inspection rounds.
    • Dispenser condition: Check whether the cabinet is bent, overloaded, dirty, or poorly positioned.
    Metric C-Fold Multifold Annual delta
    Portion control More dependent on user behavior Supported by interlocking design Depends on observed use
    Multiple-sheet risk Higher when the stack is loose or the dispenser is underfilled Lower in compatible hardware Measure locally
    Refill pressure Can rise when users pull several sheets Usually easier to control Compare refill logs
    Floor and bin waste Can increase with clumps and over-pulling Often lower when presentation works correctly Audit before and after
    Labor exposure More opportunities for jam clearing and extra checks Less dispensing intervention in suitable dispensers Record service minutes

    A supplier page on hygiene products in bulk can help organize procurement, but the decision should remain site-specific. The strongest business case comes from your own usage audit, not an assumed annual saving.

    The hidden cost is operational friction. A towel that looks cheaper on the invoice can consume more staff attention when it falls from the stack, jams at the opening, or empties before the scheduled round. Conversely, replacing compatible C-fold stock with multifold may not be sensible if the hardware is old, damaged, or incapable of supporting the new feed pattern.

    Matching the Right Fold to the Right Setting

    The best format depends on what the washroom asks users and staff to do. A private office restroom, a public school corridor, a clinic waiting area, and a food-preparation station don't create the same dispensing problem.

    A setting-by-setting decision

    Setting Recommended format Key rationale
    Home Either, based on available hardware Low complexity makes familiarity and fit more important than maximum control
    Office Multifold in compatible dispensers Clean presentation and controlled dispensing suit shared staff washrooms
    Healthcare Multifold in enclosed, compatible dispensers Reduces multiple-sheet handling and protects the remaining stack
    Food service Multifold near handwashing points Supports controlled access where adjacent sheets should remain untouched
    Education C fold in durable existing units, multifold in staff areas Hardware durability and traffic patterns differ across the building

    In a home, buying a new dispenser for a different fold may add unnecessary complexity. Choose the format that fits the cabinet you already have and that household users can load consistently.

    In an office, multifold is usually the more controlled folded option when the dispenser supports it. The interfolded presentation creates a predictable user interaction, and a neat opening makes it easier for staff to spot an empty or misloaded unit.

    Healthcare requires a sharper distinction. Use enclosed, compatible multifold dispensers in clinics, patient-facing areas, and other hygiene-sensitive locations where limiting contact with the remaining stack matters. Existing C-fold equipment may still serve a public restroom or break room, but it shouldn't be assumed to provide the same dispensing control.

    Food service has two zones. Behind the line, staff need clean, accessible hand-drying supplies that don't invite repeated contact with the stack. In a customer restroom, the priority may shift toward durability, appearance, and reliable replenishment.

    Schools often need a building-wide compromise. Student corridors may favor durable existing C-fold cabinets if replacement isn't practical, while staff-only areas can use compatible multifold dispensers. The deciding factors are user behavior, supervision, refill access, and hardware condition, not just the cheaper carton.

    For broader facilities routines, see this guide to cleaning public bathrooms. It reinforces the same operating principle: towel selection works best when it supports the whole cleaning and restocking plan.

    Making the Call and Beyond the Towel

    Use three questions to make the decision:

    1. What dispenser is already mounted? Confirm the accepted fold, opening, internal clearance, and loading direction.
    2. What is the traffic pattern? Consider steady office use separately from sharp peaks in schools, clinics, and public venues.
    3. What is the hygiene priority? If single-sheet presentation and limited contact matter most, choose compatible multifold hardware.

    Choose C-fold when an existing C-fold dispenser is reliable, the washroom needs a familiar flat-stack system, and replacing the cabinet would create unnecessary disruption. Choose multifold when the dispenser supports interlocked towels and the facility needs tighter portion control, cleaner presentation, or reduced multiple-sheet handling.

    Switching formats without changing dispensers can work in some universal units, but it can also create jams, slumping, tearing, or excess dispensing. Hardware replacement may erase the apparent product saving, so evaluate the full lifecycle rather than approving a carton based on its unit price.

    Hand drying also depends on user behavior. People need enough time, friction, and coverage to remove moisture effectively, while staff need the dispenser mounted at a practical height, the waste bin placed close enough to catch used towels, and the unit inspected before peak periods.

    A checklist infographic titled Making the Call and Beyond the Towel with customer service best practices.

    Review your current dispensers, record refill and jam events, and test the intended towel under normal use before standardizing across a building. For further virus education, prevention guidance, and evidence-led hygiene content, visit VirusFAQ.com.

  • Recreational Water Illness: What It Is and How to Stay Safe

    A family leaves a crowded public pool after a hot summer afternoon. Two days later, one child develops severe diarrhea, while everyone else wonders whether the illness came from lunch, school, or the water. That uncertainty is understandable, but recreational water deserves serious attention: a CDC-linked estimate found 5.61 million domestically acquired infectious waterborne illnesses associated with recreational water in the United States in 2014, representing 78% of an estimated 7.15 million total infectious waterborne illnesses that year. The estimated annual economic burden was $2.2 billion to $3.7 billion. (CDC-linked burden estimate)

    The lesson isn't just “don't swallow pool water.” Chlorine-tolerant parasites, aerosolized bacteria, contaminated splash venues, and untreated natural water create different routes to illness. Understanding those routes helps families, swimmers, clinicians, and facility operators choose precautions that match the actual hazard.

    What Recreational Water Illness Covers

    Recreational water illness, or RWI, describes disease or irritation caused by germs or chemicals in water used for swimming, bathing, splashing, wading, or related activities. That includes public pools, hot tubs, splash pads, decorative fountains, lakes, rivers, and oceans. (CDC definition and exposure routes)

    The same setting can create different exposures. A child with stomach cramps may have swallowed contaminated water. A swimmer with an itchy rash may have sat in a poorly maintained hot tub. Someone who stayed out of the water could still inhale mist near a spa or fountain. RWI can involve gastrointestinal, respiratory, skin, ear, and eye illness, along with less common but serious wound or neurologic disease.

    Practical rule: Ask how exposure occurred, not only where it occurred.

    Three routes explain much of the confusion:

    • Ingestion: Swallowing water contaminated with stool can transmit organisms that cause diarrhea, cramps, nausea, or vomiting.
    • Inhalation: Breathing mist or aerosols can carry bacteria from warm water or complex plumbing into the lungs.
    • Contact: Germs and irritants can reach the skin, ears, eyes, open wounds, or contact lenses.

    The scale extends beyond swimming pools. An earlier burden estimate linked recreational water with about 4 billion surface-water recreation events annually and about 90 million illnesses nationwide tied to swimming, wading, paddling, motor-boating, and fishing. Those estimates include treated and untreated water, with outcomes ranging from gastrointestinal illness to ear, eye, respiratory, and skin problems.

    The key question is what routine disinfection can control. Chlorine handles many organisms, but Cryptosporidium forms oocysts that tolerate chlorine better than many other germs. Legionella can grow in plumbing biofilms and spread through aerosols from warm-water systems. In practice, swimmers may need to avoid swallowing water, stay away from hot-tub mist, and follow facility closures, while operators need maintenance, engineering controls, and outbreak procedures. A chlorine reading alone cannot answer every safety question.

    For a broader explanation of how disease-causing organisms move between hosts, see this overview of what a pathogen is.

    The Five Pathogens Behind Most U.S. Outbreaks

    CDC surveillance identifies Cryptosporidium, Pseudomonas, Legionella, Shigella, and norovirus as the leading causes of reported U.S. recreational water outbreaks from 1971 through 2020. (CDC prevention guidance) Their different survival and transmission patterns explain why a chlorine reading cannot answer every safety question.

    Cryptosporidium parvum and Cryptosporidium hominis mainly spread through the fecal-oral route. An infected swimmer can release oocysts into the water, and another person may become ill after swallowing a small amount. Crypto matters especially in pools and water parks because its oocysts tolerate routine chlorine levels better than many other germs. Treated venues recorded 76 Cryptosporidium outbreaks and 2,492 cases from 2015 through 2019. (CDC outbreak report) That resistance makes fecal-source control, staying out of the water while ill, and proper response to contamination more important than relying on chlorine alone.

    Legionella pneumophila follows a different route. It can multiply in warm water and plumbing biofilms, then spread when people inhale contaminated aerosols. Hot tubs, spas, decorative fountains, and poorly managed large plumbing systems can generate the mist that carries the organism. The same CDC surveillance period recorded 65 treated recreational water outbreaks and all 13 deaths. For swimmers, the behavior change is specific: avoid breathing hot-tub mist, especially when a facility has maintenance or closure warnings.

    Pseudomonas aeruginosa persists in wet environments and hot-tub biofilm. It commonly causes hot-tub folliculitis, an itchy rash around hair follicles, and can contribute to otitis externa, often called swimmer's ear. Shigella species and norovirus spread through fecal contamination. Shigella can move efficiently through splash pads and wading pools, while norovirus can spread through vomit and stool contamination in hotels, cruise environments, and shared aquatic facilities. For concise clinical terminology, see these infectious disease clinical notes, along with this guide to norovirus transmission.

    Pathogen Type Primary transmission route Typical recreational setting
    Cryptosporidium Protozoan parasite Swallowing contaminated water Pools, water parks, splash venues
    Legionella pneumophila Bacterium Inhaling contaminated aerosols Hot tubs, spas, fountains
    Pseudomonas aeruginosa Bacterium Skin or ear contact with contaminated water Hot tubs, pools
    Shigella species Bacterium Fecal-oral transmission Splash pads, wading pools
    Norovirus Virus Ingestion of contaminated water, food, vomit, or stool particles Communal aquatic settings

    The prevention priority depends on the pathogen. Crypto and enteric viruses require strong fecal-source control. Legionella requires control of warm-water aerosols. Pseudomonas requires attention to wet biofilm. Each one points to a different action, so “chlorinated” does not mean every exposure route is equally protected.

    How Symptoms Differ by Exposure Route

    A symptom pattern often points to the way contaminated water entered the body. Diarrhea after swallowing pool water suggests a different exposure from a rash after using a hot tub, while pneumonia after breathing spa mist raises concern about an aerosolized pathogen.

    Ingestion

    Swallowing contaminated water can cause watery diarrhea, abdominal cramps, nausea, and vomiting. Cryptosporidiosis may persist for two weeks. Norovirus and Shigella often cause a more sudden gastrointestinal illness that begins within roughly 24 to 72 hours of exposure. These time windows offer useful clues, but they cannot replace testing or medical evaluation.

    Source control matters because a person with diarrhea may contaminate water even after feeling well enough to swim. A small swallowed amount can also carry enough organisms to cause illness. The CDC prevention guidance identifies diarrhea as the most common cause of recreational water outbreaks and advises people with Crypto to stay out of the water for two weeks after symptoms stop.

    Inhalation

    Breathing contaminated mist produces a different clinical picture. Pontiac fever can cause a flu-like illness that is generally self-limited. Legionnaires' disease can cause pneumonia, high fever, cough, and chest pain. Respiratory symptoms after hot-tub or spa exposure warrant prompt medical attention, especially for someone who is pregnant, immunocompromised, or living with lung disease.

    A person does not need to swim to encounter this route. Someone standing beside a bubbling spa or decorative fountain can inhale aerosolized water without swallowing it. Ventilation, water-temperature management, plumbing maintenance, and aerosol control therefore matter alongside disinfection. Chlorine may reduce some hazards, but it does not make every mist exposure safe.

    Skin and mucosal contact

    Pseudomonas hot-tub folliculitis commonly appears as itchy red bumps beneath a swimsuit. Water trapped in the ear canal can contribute to swimmer's ear, and contaminated water entering an open wound can cause a more serious infection. Organisms or chemicals may irritate the eyes. Contact-lens wearers face added concern from rare but potentially severe corneal infections, including Acanthamoeba keratitis.

    A chlorine reading can be reassuring, but it cannot identify every exposure route or remove every hazard immediately. A strong reading also does not erase the need to manage warm-water aerosols, wet surfaces, and fecal contamination according to the pathogen involved.

    Seek medical advice if symptoms worsen, breathing problems develop, severe eye pain occurs, a wound becomes red or swollen, or fever accompanies a rash. People with chronic lung disease, pregnancy, weakened immunity, or other significant medical conditions should seek care sooner.

    Diagnosis, Reporting, and Treatment Pathways

    Clinicians start with the exposure history. They'll ask whether the patient swallowed water, used a hot tub, inhaled spray, developed symptoms after a fecal incident, or shared a facility with others who became ill. Timing, symptom pattern, travel, underlying conditions, and recent antibiotic use can all shape the next step.

    Testing follows the suspected route

    For diarrhea and vomiting, stool molecular panels can detect organisms such as Cryptosporidium, Shigella, and norovirus. A clinician may order targeted testing when an outbreak is suspected or when symptoms are severe, prolonged, bloody, or associated with fever.

    Respiratory illness after a spa or hot-tub exposure may prompt a sputum culture and a urinary antigen assay for Legionella. Pseudomonas can be investigated by culturing material from an ear, wound, or respiratory specimen when the clinical picture warrants it. A rash that clearly fits uncomplicated hot-tub folliculitis may not require extensive testing, but persistent, spreading, or systemic symptoms change that calculation.

    Treatment depends on severity

    Many viral gastrointestinal illnesses receive supportive care, especially careful replacement of fluids and electrolytes. Cryptosporidiosis also often requires hydration and monitoring, while nitazoxanide may be considered for severe cases under medical guidance. Legionella pneumonia requires prescription antibiotics, commonly a macrolide or fluoroquinolone selected by the treating clinician. Pseudomonas folliculitis is often managed with topical care, but extensive infection or a high-risk patient may need a different approach.

    Seek care promptly for: bloody diarrhea, high fever, respiratory symptoms after hot-tub exposure, severe dehydration, or a rash accompanied by fever.

    Public-health reporting matters even when one patient improves. State health departments can connect apparently separate cases and report outbreaks through CDC's Waterborne Disease and Outbreak Surveillance System. That process helps identify contaminated venues, recurring equipment failures, and pathogens that routine testing may miss.

    Don't return to a pool or spa while you have diarrhea. Tell the facility and your healthcare professional about the exposure, especially if other swimmers are sick. Early reporting can protect people who haven't developed symptoms yet.

    Why Pools, Hot Tubs, Lakes, and Oceans Carry Different Risks

    “Swimming” describes an activity, not a single risk category. A cool, treated pool, a warm spa, a recirculating splash pad, and a river after heavy rain expose people to different combinations of temperature, circulation, contamination, and monitoring.

    Pools generally use chlorine or bromine, and operators can measure the water's disinfectant residual. That control reduces many risks, but it doesn't make the venue sterile. Crypto can resist routine chlorine levels, and a fecal incident can contaminate a large shared volume before staff recognize it.

    Hot tubs add warmth and aerosol production. Higher temperatures can make disinfectant management more difficult, while jets create inhalable mist. Those conditions favor concern about Legionella and Pseudomonas, especially when plumbing, filtration, turnover, or cleaning is inadequate. A decorative fountain may create a similar aerosol concern without looking like a swimming venue.

    Splash pads and interactive fountains create a different challenge. Children touch wet surfaces, sit in shallow water, and may put their hands in their mouths. Recirculated water can spread contamination across many contact points, so operators need close monitoring and strong fecal-incident procedures.

    Setting Disinfection Dominant pathogen concerns Highest-risk group
    Pool Chlorine or bromine, with a measurable residual Cryptosporidium and fecal-oral pathogens Young children, swimmers with diarrhea
    Hot tub or spa Chlorine or bromine in warm, aerated water Legionella and Pseudomonas Older adults, people with lung disease, frequent spa users
    Splash pad or fountain Recirculated treated water, often with heavy hand and surface contact Cryptosporidium, Shigella, norovirus Young children and families
    Lake or river No residual disinfectant, local advisories and sampling Giardia, Campylobacter, and other untreated-water hazards Campers, paddlers, swimmers who swallow water
    Ocean or coastal water No residual disinfectant, beach monitoring and advisories Local microbial and runoff-related hazards People with open wounds and those entering after contamination events

    Natural water deserves a separate mental model. Surveillance found 32 outbreaks linked to ingesting insufficiently treated freshwater sources in 16 jurisdictions from 2000 through 2022, causing 437 illnesses. Giardia was implicated in 69% of outbreaks, Campylobacter in 28% of cases, rivers or streams in 75% of outbreaks, and half of the outbreaks involved no treatment attempt. (Freshwater outbreak surveillance)

    Before coastal recreation, readers should check local conditions, recent rain, runoff, and advisory information. Guidance such as this explanation of snorkeling Kona after rain is useful because rainfall can change visibility, runoff, currents, and exposure conditions even when the water looks inviting.

    Disinfection Standards That Protect Swimmers

    Disinfection has a narrow operating window. CDC-aligned guidance recommends a pH of 7.2 to 7.8, with free chlorine at at least 1 ppm in pools and at least 3 ppm in hot tubs and spas. If cyanuric acid is used, pools should have at least 2 ppm free available chlorine. (CDC-aligned disinfectant guidance)

    pH controls how well chlorine works. Temperature, sunlight, swimmer load, organic material, filtration, and water replacement also change performance. A test can show an acceptable reading while contamination remains, especially after fecal shedding, heavy use, or biofilm growth in plumbing.

    An infographic showing disinfection standards for pools and hot tubs, including pH levels, chlorine concentrations, and testing frequency.

    What operators should verify

    Operators should keep written pH and free-chlorine logs, test more often during busy periods, monitor combined chlorine, and respond promptly to fecal incidents. Hyperchlorination may be required after contamination. The correct response depends on the organism, water volume, filtration, cyanuric acid use, and local code.

    Crypto shows why routine readings cannot settle every risk. Its oocysts tolerate ordinary pool conditions better than many common germs, so a confirmed event can require a more intensive response. Suitable venues may use specialized procedures or secondary systems such as ultraviolet treatment. Facilities comparing equipment can review modern pool water treatment systems, while remembering that technology does not replace trained staff or exclusion policies.

    What swimmers can do

    Swimmers should shower before entering, use bathroom breaks, avoid urinating in the water, and stay out while ill with diarrhea. Ask whether staff check pH and disinfectant levels and whether the facility follows a documented fecal-incident policy. The explanation of contact time for disinfectants clarifies why a chemical needs enough contact with a germ before it can work.

    Chlorine reduces many hazards when managed correctly, but it is not a universal shield. Crypto may persist through routine treatment, while Legionella and Pseudomonas require attention to warm-water plumbing, contamination sources, aerosols, and recovery procedures. Hot tubs deserve extra caution because bubbling can spread contaminated droplets through the air, making ventilation and maintenance part of swimmer protection.

    Prevention Habits That Stop Outbreaks Before They Start

    Outbreak prevention works through three connected actions: disrupt contamination, disinfect the environment, and exclude infectious swimmers. Showering removes fecal material before it enters the water. Chemical treatment reduces many organisms that do enter it. Keeping ill swimmers away prevents fresh contamination while they are infectious.

    An infographic illustrating three key prevention habits: showering, disinfecting pool chemicals, and avoiding swimming when ill.

    Disrupt the contamination cycle

    Make these habits routine:

    • Shower first: Wash with soap before entering, particularly after outdoor play or bathroom use.
    • Schedule bathroom breaks: Take young children out regularly to reduce accidents.
    • Protect the water: Keep anyone with diarrhea out of pools, splash pads, and other shared water.

    Swimmers should avoid swallowing water, keep wet hands away from the mouth, and cover open wounds with a waterproof dressing or stay out of the water. Shower with soap after swimming, remove wet swimwear, and dry ears carefully. Contact-lens users should keep lenses away from recreational water.

    Disinfect and inspect

    Ask how the facility measures pH and free chlorine, and what staff do after a fecal incident. Avoid hot tubs that are cloudy, slimy, strongly chemical-smelling, or missing visible maintenance information. A strong odor can signal irritating combined chlorine rather than especially clean water.

    Operators need trained staff, calibrated testing equipment, written incident procedures, and supplies for cleanup. Hot tubs and decorative fountains require controls for warm water, stagnation, aerosols, plumbing biofilm, and ventilation. Splash venues also need measures for recirculation, hand contact, diapers, and shallow-water contamination. Chlorine tolerance varies by pathogen, so routine chemical readings cannot address every risk. Bubbling can carry contaminated droplets into the air, which makes ventilation a direct health measure.

    Exclude illness

    People with diarrhea should stay out of shared water until they recover. Those with Crypto should follow CDC's two-week exclusion after symptoms stop. Swim clubs, hotels, gyms, and public pools should publish sick-swimmer policies so families know when to stay out.

    The rule applies to staff as well. Facilities should close or restrict access when contamination or an outbreak requires it, explain the decision to patrons, and involve public-health officials when several people develop compatible symptoms. VirusFAQ.com offers educational material on viral transmission and prevention, but it does not replace advice from healthcare professionals or health departments.

    Match prevention to the pathogen and exposure route. Before swimming, check the facility's water-quality information, ask about illness and fecal-incident policies, shower first, and stay out while sick. Seek medical advice for diarrhea, fever, breathing symptoms, severe eye pain, or a spreading rash after water exposure, and mention the venue and exposure route.

  • Best Hand Sanitizer for Norovirus What Works

    Most hand sanitizers are a poor answer to norovirus. That sounds surprising because alcohol sanitizer is useful against many viruses, but norovirus is a small, non-enveloped virus with a hard protein shell. The practical question isn't whether a bottle contains alcohol. It's which alcohol, at what concentration, in what formulation, with what contact time.

    The clearest starting point is still soap and running water. The CDC's hand hygiene guidance says sanitizer alone doesn't work well against norovirus and recommends washing for at least 20 seconds, especially after using the toilet or changing diapers and before eating or preparing food.

    Yet “sanitizer doesn't work” is also too simple. CDC guidance identifies ethanol-based products at 60–95% as the preferred sanitizer option during norovirus outbreaks, while acknowledging that direct evidence against human norovirus remains incomplete. Recent laboratory findings add an important detail: acidic alcohol formulations can perform very differently from alkaline formulations.

    The comparison below gives the practical answer before the deeper virology. It separates the first-choice method, the most reasonable backup, and non-alcohol options that shouldn't be treated as equivalent.

    Hygiene Method Mechanism Against Norovirus Evidence of Reduction Best Use Context
    Soap and running water Physically lifts contamination from hands and rinses it away CDC guidance reports a 0.7–1.2 log10 reduction after 20 seconds in finger-pad studies, CDC evidence First choice after toileting, diaper changes, suspected exposure, and before food
    Ethanol-based sanitizer Alcohol disrupts or damages susceptible viral particles, but performance varies by formulation Commercial alcohol products produced more than 0.5 log10 reduction, with most approaching about 2 log10 in comparative testing, CDC norovirus guidance Adjunct when soap and water aren't available
    Acidic alcohol formulation Combines ethanol activity with a low-pH environment that may improve inactivation A 2025 in vitro study completely inactivated human norovirus GII.17 within 30–60 seconds, study record A potentially stronger formulation, provided the label supports the claim
    Non-alcohol antiseptics Uses agents such as benzalkonium chloride, triclosan, or chlorhexidine Older reviews cited by CDC found these agents ineffective in several norovirus studies, CDC norovirus guidance Not a preferred norovirus strategy

    Introduction Why Hand Sanitizer Alone Is Not Enough for Norovirus

    The popular advice is to keep sanitizer nearby and use it whenever washing isn't convenient. That advice makes sense for many everyday exposures, but it can mislead people during a norovirus outbreak. A quick application of a standard sanitizer shouldn't make you assume that contaminated hands are now safe.

    Norovirus spreads through tiny amounts of fecal material or vomit reaching the mouth. Hands can pick up contamination after toileting, diaper changes, caregiving, cleaning, or touching contaminated surfaces. Sanitizer may reduce some viral material, but a reduction in detectable virus isn't the same as dependable prevention of infection.

    That distinction matters because norovirus lacks the lipid envelope that makes many other viruses more vulnerable to alcohol and detergents. The outer protein shell gives it greater stability, so the product category alone can't predict performance. The broader explanation of whether hand sanitizer kills viruses is useful background, but norovirus needs its own decision rule.

    The practical hierarchy

    Think of the choices in this order:

    1. Soap and running water, used correctly, remains the benchmark.
    2. Ethanol sanitizer between 60% and 95% is the preferred alcohol option when washing isn't possible, especially during an outbreak.
    3. Non-alcohol antiseptics shouldn't be assumed to provide comparable norovirus protection.
    4. Product-specific formulation details matter. pH, inactive ingredients, application time, and testing method can change the result.

    The short answer: The best hand sanitizer for norovirus is an ethanol-based formulation in the CDC's preferred range, but it remains an adjunct. It isn't a replacement for thorough handwashing.

    Families need a simple plan they can follow under pressure. Clinicians and infection-control teams need a more careful interpretation of the evidence, because results differ across products, viral strains, and laboratory models. This guide addresses both needs, starting with why norovirus behaves differently, then comparing hygiene methods, interpreting formulation claims, and applying the evidence at home, in schools, during travel, and in healthcare settings.

    Understanding Norovirus and Why It Resists Many Disinfectants

    Norovirus belongs to the Caliciviridae family and is a small, non-enveloped virus. “Non-enveloped” means it doesn't have the outer fatty membrane found in viruses such as influenza and SARS-CoV-2. Instead, norovirus is protected by a protein capsid, a structure that can tolerate conditions that damage more fragile enveloped viruses.

    That biology doesn't mean norovirus is immune to disinfection. It means the method must match the pathogen. Alcohol can work inconsistently against non-enveloped viruses, and ordinary detergents or low-level antiseptics may not disrupt the capsid sufficiently. The scientific overview of norovirus transmission, environmental persistence, and disinfection provides further context for that stability.

    Norovirus also isn't one perfectly uniform target. Researchers describe multiple genogroups and strains, with GII.4 commonly associated with human disease. Recent testing has also examined human norovirus GII.17, and its response to an alcohol disinfectant differed according to formulation pH. That strain-specific behavior is one reason a blanket statement about every alcohol sanitizer can be misleading.

    An infographic titled Understanding Norovirus explaining its characteristics, survival mechanisms, resistance, and proper disinfection methods.

    How contamination reaches the mouth

    The main route is fecal-oral transmission. A person touches contaminated material, then transfers the virus to food, utensils, a phone, a doorknob, or directly to their mouth. Vomiting creates an additional cleaning challenge because droplets and particles can contaminate nearby hands and surfaces.

    The virus doesn't need to behave like a respiratory virus to move efficiently through a household or institution. Shared bathrooms, caregiving, food preparation, and high-touch objects create repeated opportunities for transfer. Sanitizing hands is therefore only one part of control. Cleaning contaminated surfaces, handling laundry carefully, and keeping sick people away from food preparation also matter.

    Why “kills viruses” isn't enough

    A label may advertise broad antiviral activity, but that wording doesn't automatically establish reliable performance against norovirus. Testing can use different strains, contact times, surfaces, and surrogate viruses. A product that performs well in one setup may not produce the same result on wet, dirty, or heavily contaminated hands.

    For readers comparing products, the meaningful questions are narrower: Does the product use ethanol? Is the concentration stated? Does the manufacturer provide norovirus-specific testing? Does the claimed contact time reflect real use? Those questions are more informative than a general claim that a product is “antibacterial” or “antiviral.”

    How Soap and Water Alcohol Sanitizers and Non Alcohol Options Compare

    Soap and water remains the clearest choice for norovirus because it removes contamination rather than asking a chemical to inactivate every particle. Soap loosens oils and organic material, while running water carries the loosened material away. The process is closer to rinsing grit from a surface than neutralizing it in place.

    Finger-pad evidence found that 20 seconds of soap-and-water washing reduced norovirus by 0.7–1.2 log10. The CDC outbreak report also describes alcohol-based sanitizers as less consistent in that evidence base. For families and clinicians, the practical hierarchy is straightforward: wash when facilities are available, use sanitizer as a temporary measure when they are not, and avoid assuming that every alcohol-free product offers the same protection.

    Ethanol products offer partial help

    “Partial” means a sanitizer may lower the amount of virus on the hands without removing or inactivating enough to make handwashing unnecessary. In comparative testing, alcohol-based products produced reductions greater than 0.5 log10, while most approached about 2 log10 for the tested material. Those results describe measured performance under study conditions, not a guarantee for every product or real-world hand.

    The difference matters at the point of use. A small remaining amount can still transfer to food, a utensil, a phone, or the mouth. Wet, visibly dirty, or heavily contaminated hands also change the exposure: soil can shield virus, and incomplete coverage leaves untreated areas. Sanitizer is therefore best understood as a bridge until soap and running water are available, not as an equivalent replacement.

    Product formulation adds another layer. Ethanol percentage matters, but pH, ingredients that slow evaporation, and the time the hands remain wet can change how much exposure the virus receives. Two products with similar alcohol labels may not perform identically, so norovirus-specific testing is more informative than a broad “antiviral” description.

    Non-alcohol options are not equivalent

    Benzalkonium chloride, triclosan, and chlorhexidine occur in various antiseptic products, yet older reviews found poor or ineffective norovirus performance for these ingredients in several studies. That finding does not prove that every formulation behaves identically under every test condition. It does mean these products should not be treated as interchangeable with soap and water or a tested ethanol formulation.

    The relevant question is not whether a product is alcohol-free. It is whether its exact formulation has evidence against norovirus, under conditions resembling actual hand use. A product may support general hand hygiene while offering limited value against this virus. For a focused discussion of whether alcohol-free hand sanitizers work, examine the ingredient, testing method, contact time, and stated target before choosing it.

    What Makes an Ethanol Sanitizer More Effective Against Norovirus

    The label “alcohol-based” does not settle the norovirus question. Ethanol concentration matters, but pH, supporting ingredients, evaporation, hand coverage, and wet contact time determine how much exposure the virus receives. Two products with similar ethanol percentages may therefore behave differently.

    A 2025 in vitro study shows why pH deserves attention. An acidic alcohol-based disinfectant completely inactivated human norovirus GII.17 within 30–60 seconds, while an alkaline alcohol-based disinfectant failed to inactivate the same strain even at 60 seconds. This result does not show that every acidic product works against every norovirus strain. It does show that “contains alcohol” is an incomplete screening rule. The detailed results are available in the PubMed study record.

    A hand hygiene guide infographic showing recommendations for using hand sanitizer and soap in various environments.

    Concentration and formulation work together

    Fingerpad testing compared an engineered 70% ethanol hand sanitizer with a 75% ethanol control. After 30 seconds, the engineered formulation achieved a 2.48 log10 reduction of murine norovirus, while the control achieved 0.91 log10, a difference of more than 1.5 log10 on that surrogate model.

    The comparison makes the formulation point clear. A higher ethanol percentage does not automatically produce better norovirus performance. Surrogate-virus results also do not equal direct testing against human norovirus, so they describe how a formulation performed under a particular test rather than promising the same result for every product.

    How to assess a product label

    Read the label for details that help explain how the product was tested and how it should be used:

    • The stated ethanol concentration, so you can compare the formula with the CDC-preferred range.
    • A defined contact time, meaning the period the hands must remain visibly wet.
    • Norovirus-specific testing, rather than a general claim about bacteria or germs.
    • pH disclosure or other formulation details, when provided.
    • Clear directions, intact packaging, and storage information that support proper product performance.

    Manufacturers may not disclose enough information to compare pH or inactive ingredients. If those details are missing, favor an ethanol product with clearer norovirus-specific documentation, while keeping expectations modest. No formulation eliminates the need for soap and running water after suspected contamination.

    When to Use Each Option in Real World Situations

    The right choice depends on what happened and what facilities are available. A person leaving a bathroom with access to a sink should wash. A traveler seated far from a sink may use ethanol sanitizer temporarily, then wash at the next opportunity. During an outbreak, that distinction becomes more important because repeated small transfers can maintain spread.

    A checklist infographic illustrating decision-making criteria for choosing between DIY, professionals, buying new or used, and alternatives.

    Home care

    At home, place handwashing at the moments that matter most: after toileting, after changing a diaper, after caring for someone with vomiting or diarrhea, and before eating or preparing food. If a sink isn't immediately available, an ethanol product in the CDC-preferred range is a reasonable temporary measure, but washing should follow as soon as possible.

    Caregivers should also avoid preparing food for others while ill. Hand hygiene can't compensate for contaminated food handling, and sanitizer shouldn't be used to create false confidence after cleaning vomit or fecal material.

    Schools and childcare

    Children need frequent supervised handwashing, particularly after bathroom use and before meals. Sanitizer can serve as a supplement when a sink is unavailable, but staff shouldn't present it as an equivalent substitute.

    A school or childcare center should pair hand hygiene with environmental cleaning and clear exclusion policies for symptomatic people. Norovirus control fails when staff focus on hands while overlooking contaminated bathrooms, shared objects, food service, or cleanup procedures.

    Cruise travel and other trips

    Travelers may carry an ethanol sanitizer for moments when washing isn't possible. During an outbreak, use it as a bridge before meals or after touching shared surfaces, then wash thoroughly at the next sink.

    Practical travel rule: Sanitizer is a backup for access problems, not permission to skip washing after a high-risk exposure.

    Healthcare and food preparation

    Healthcare workers should follow facility protocols, including appropriate protective equipment and handwashing when hands are visibly soiled. Food handlers should rely on soap and water before preparing food. Sanitizer can support general hygiene in some workflows, but it isn't a substitute for washing before food handling or after suspected norovirus contamination.

    The CDC characterizes the evidence for alcohol-based sanitizers against human norovirus as very low quality and calls for more direct evaluation, as described in its norovirus evidence review. That uncertainty shouldn't paralyze decisions. It means the strongest recommendation remains consistent: wash when you can, and choose ethanol rather than a non-alcohol formula when you can't.

    How to Choose and Use Hand Hygiene Products Correctly

    Correct technique determines how much protection a hand sanitizer can provide. Apply enough ethanol sanitizer to keep both hands visibly wet, then rub methodically across palms, backs of hands, between fingers, fingertips, thumbs, and around the nails. These areas are easy to miss, much like wiping only the center of a tabletop while leaving its edges untouched.

    Keep rubbing until the product dries on its own. Wiping it away early shortens the wet contact period, giving the formulation less time to act. If hands dry almost immediately, too little product was probably used.

    Washing remains the critical step

    Use running water and plain or antiseptic soap for at least 20 seconds, following established handwashing guidance. Wash after using the toilet, changing diapers, cleaning up illness, and before eating or preparing food. Sanitizer is not designed to replace washing when hands are visibly contaminated.

    Common technique errors include covering only the palms, using too little product, and touching objects before hands are fully dry. As covered above, non-alcohol wipes are not a proven norovirus substitute for washing.

    For a practical kit, keep soap available at home, an ethanol sanitizer for travel or sink-free moments, disposable towels, and products intended for contaminated surfaces. A wipe format may help with portability or controlled application. Spectrum Hand Sanitizer Wipes are one product resource to evaluate by its active ingredient, intended use, and label directions. Apply hand products to every surface, allow the stated wet time, and wash at the next available sink.

    Practical Recommendations and What to Keep at Home

    A useful home plan separates primary protection from backup options. Use this hierarchy:

    • Choose soap and running water first. Wash for at least 20 seconds after toileting, diaper changes, suspected contamination, and before handling food.
    • Keep an ethanol sanitizer available as an adjunct. Choose the CDC-preferred ethanol range when a sink is unavailable, particularly during an outbreak. Treat sanitizer as a bridge to washing, not a replacement for it.
    • If you already own a benzalkonium-based antiseptic, keep it for general hygiene according to its label, but buy an ethanol product for norovirus outbreak preparedness.
    • Prefer product-specific evidence. Look for testing against human norovirus or a clearly identified norovirus surrogate, then follow the stated contact time.
    • Treat pH as a meaningful variable. Recent testing found a major difference between acidic and alkaline alcohol formulations. Ethanol percentage alone cannot predict how well every product will perform.

    Before buying, check four label details: active ingredient, concentration, norovirus-related testing or claims, and required wet contact time. Store products where adults can reach them quickly, keep the label readable, and replace containers that are empty, damaged, or past the labeled expiration date. A small kit can include soap, sanitizer, disposable towels, and a surface product labeled for norovirus.

    Evidence remains incomplete and strain-dependent. If several people become ill, contact local public health authorities or a healthcare professional for setting-specific guidance. Seek medical advice promptly for dehydration, worsening symptoms, vulnerable household members, or uncertainty about care.

  • Incubation Period for Hand Foot and Mouth Disease

    The typical incubation period for hand, foot, and mouth disease is 3 to 6 days, and most cases show up within roughly a week of exposure. In real life, that means a child exposed early in the week might seem completely fine for several days, then develop fever or mouth pain before the weekend is over.

    That short window is why hand, foot, and mouth disease can feel so sudden. A toddler plays normally at daycare on Tuesday, eats dinner like usual that night, and then wakes up Friday warm, clingy, and uninterested in breakfast. By Monday, the mouth sores are obvious, the hand rash has appeared, and everyone is trying to work backward to figure out when exposure happened.

    Parents often get stuck on one question: “If my child was exposed, when should I expect symptoms?” Clinicians ask a slightly different one: “How far back should I trace contacts, and how long should I watch the class or household?” The answer starts with the familiar 3 to 6 day figure, but it gets clearer when you look at how the timing is distributed, how official guidance differs slightly across countries, and why some children fall a little earlier or later than the textbook average.

    When Symptoms Usually Show Up After Exposure

    A common daycare pattern looks like this. One child attends on Tuesday with no obvious symptoms. By Friday, that child develops fever. The following Monday, mouth ulcers and the classic hand or foot rash make the diagnosis much more obvious.

    That timeline fits hand, foot, and mouth disease well. The CDC lists the incubation period as 3 to 6 days in its Yellow Book entry on hand, foot, and mouth disease. In practical terms, most children who catch the virus from a known contact will start showing something within about a week.

    A short clock, not an instant switch

    People get tripped up. They hear “3 to 6 days” and imagine a fixed countdown, as if symptoms should begin exactly on day 4 or day 5. That's not how incubation works. It's a range, and ranges reflect variation in real children, real exposures, and different circulating enteroviruses.

    A household example makes this easier to picture. If an older sibling brings HFMD home on Sunday, a younger sibling who catches it might not show fever on Monday or Tuesday. But if Friday comes and that younger child is newly refusing drinks, drooling, or developing sores, that timing still fits the expected window well.

    Practical rule: If you know the exposure date, pay the closest attention over the next week, especially from the middle of that window onward.

    Why the first symptom may not be the rash

    Another source of confusion is that parents often expect the hand and foot spots to be the first sign. They usually aren't. Early symptoms can be vague. A child may first seem tired, fussy, warm, or less interested in eating and drinking. The more recognizable rash often arrives after that.

    A CDC-adapted public health fact sheet notes that symptoms usually appear 3 to 7 days after infection, and that fever is often the first symptom to appear in this public health fact sheet. That's why an exposure often “reveals itself” first as fever or sore mouth, not as visible blisters.

    What the Incubation Period Actually Means

    Incubation period means the time between catching the virus and the first symptom. If your child shares toys, saliva, or contaminated hands with an infected child today, the incubation period is the stretch of days before fever, mouth pain, or rash begins.

    That sounds simple, but it's easy to mix up with two other ideas: the latent period and the infectious window. If you want a general primer on the term itself, VirusFAQ has a basic explainer on what an incubation period is.

    Incubation period versus latent period

    The incubation period is about when symptoms start. The latent period is about when the body begins shedding enough virus to infect others. Those two clocks are related, but they aren't identical.

    That distinction matters because a child can carry the virus before anyone realizes they're sick. A parent is often focused on symptom timing. A clinician, school nurse, or outbreak investigator also has to think about who may have been exposed before diagnosis was obvious.

    Incubation period versus infectious window

    The infectious window is the period when a person can spread the virus to others. It overlaps with the end of incubation and continues after symptoms begin. That's why exclusion rules for daycare or school can't rely only on “How many days has it been since exposure?”

    Here's the practical breakdown:

    • Parents use incubation timing to decide when to watch closely after a known exposure.
    • Clinicians use infectious timing to think about who else may have caught it.
    • Schools and childcare programs use symptom status to decide when a child should stay home or return.

    The incubation clock answers, “When might illness begin?” It doesn't answer, by itself, “When is spread no longer possible?”

    Why this matters in real conversations

    If a daycare tells a parent that a classmate had HFMD, the parent usually wants a calendar answer. If a pediatric clinician hears that several children developed similar symptoms across one classroom, the clinician wants a transmission answer. Same disease, different question.

    That's also why age can matter. Younger children and older children don't always sit at the exact same point inside the broader incubation window.

    Typical and Outer Ranges for HFMD Incubation

    A parent hears about an exposure at daycare on Thursday and wants one answer: “What day should I worry most?” The honest answer is a range with a center and edges. For hand, foot, and mouth disease, the center is usually a few days after exposure, but public-health guidance leaves room on both sides of that middle.

    When the curve is busiest

    The familiar number is 3 to 6 days. That remains a practical starting point because several guidance sources cluster there. A 2024 overview from China CDC's HFMD summary pulls together estimates that sit close to one another: an AAFP review at 3 to 6 days, China CDC's own description of 2 to 10 days with an average of 3 to 5 days, and Singapore guidance listing a typical range of 3 to 5 days with an outer range of 2 to 14 days.

    That pattern matters because incubation works less like a deadline and more like a bell-shaped curve. Many children who become sick will do so near the middle of the window. Fewer show symptoms very early or much later, but those later cases still matter when a classroom or household is being watched closely.

    Why the outer limits change decisions

    If a child was exposed five days ago and now has fever or mouth pain, that timing fits the common pattern. If day 8 passes without symptoms, concern drops. It does not disappear.

    That is the part short summaries often miss.

    For routine home monitoring, families often focus on the middle of the range because that is where illness is most likely to declare itself. For daycare exclusions, sibling exposures, or cluster investigations, the tail of the curve matters more. A longer outer range means a child can fall outside the textbook average and still fit a known exposure, which is why contact tracing cannot stop at day 6 just because many articles do.

    Source Reported Range Practical Takeaway
    CDC 3 to 6 days Good shorthand for routine counseling after a single exposure
    China CDC 2 to 10 days, average 3 to 5 days Shows a wider surveillance window around the usual midpoint
    Singapore guidance 2 to 14 days, typical 3 to 5 days Useful when advising families or schools about later outliers
    AAFP review 3 to 6 days Supports the familiar clinical estimate

    How to use this without turning every exposure into a two-week alarm

    A simple calendar approach helps.

    • Watch most closely during the first week after exposure. That is where the heaviest part of the curve sits.
    • If symptoms appear earlier or later, compare them with the full range, not only the average. That keeps a real exposure from being dismissed too quickly.
    • Use the wider outer window for outbreak work, not panic. It is mainly for settings like daycare rooms, households, and linked cases where timing affects who gets notified and how long people are observed.

    For parents, the middle of the range answers “When is illness most likely to start?” For clinicians and childcare staff, the tails answer a different question: “How long could this exposure still plausibly explain a new case?”

    How Virus Type and Age Shift the Timeline

    Not every child sits in the same spot inside the incubation window. Surveillance data suggest that age shifts the median timing, and that's one reason “3 to 6 days” should be treated as a guide, not a stopwatch.

    A peer-reviewed study using surveillance data from children in China found median incubation periods of 4.4 days in kindergarten students, 4.7 days in primary-school students, and 5.7 days in secondary-school students in this PMC study on HFMD incubation modeling. Another estimate discussed in the same evidence base found a median of 5.4 days with a 95th percentile of 14 days.

    Age group comparison

    Those numbers suggest a subtle pattern. Younger children tend to cluster a bit earlier, while older children can run later within the broader expected range.

    Age Group Median Incubation (days) Range (days) Predominant Virus
    Kindergarten 4.4 Not specified in age row Not specified
    Primary school 4.7 Not specified in age row Not specified
    Secondary school 5.7 Not specified in age row Not specified
    Overall in one surveillance model 5.7 1.3 to 15.2 Not specified

    That helps explain why some parents of toddlers feel the illness “moved fast,” while clinicians following school-aged contacts may keep a longer watch window in mind.

    Why parents of older children sometimes get mixed messages

    Many online explanations focus on toddlers because HFMD is mainly a young-child infection. But older children and adults can still get it, and the timeline may feel less textbook in those groups. If you're also wondering how this illness can look outside the classic preschool setting, VirusFAQ has a separate overview on adult hand, foot, and mouth disease.

    A median isn't a deadline. It marks the middle of the pattern, not the point after which cases stop appearing.

    What we can say, and what we shouldn't overstate

    The evidence you can act on is clear enough: age appears to shift the center of the curve slightly. What we shouldn't do is pretend that every younger child will show symptoms early or every older child will show them late. Real families still see overlap.

    From First Fever to Full Symptom Picture

    Once the incubation period ends, symptoms usually don't appear all at once. The illness often unfolds in a sequence that feels messy to parents but familiar to clinicians.

    A timeline graphic illustrating the Hand-Foot-and-Mouth Disease incubation period and symptom progression from exposure to recovery.

    What usually appears first

    In many children, the first obvious change is fever, fussiness, sore throat, or reduced appetite. That early stage can look like a generic viral illness. A child may want fewer solids, more cuddling, and less activity before anyone sees a single spot.

    After that, the mouth often becomes the clue. Parents notice drooling, refusal of acidic foods, or crying with swallowing. Only then do the hands, feet, or diaper area make the diagnosis easier to spot.

    A usable home timeline

    A simple way to think about the progression is this:

    • Early symptom phase: fever often leads
    • Shortly after: sore throat, irritability, lower appetite
    • Then: mouth sores become more obvious
    • After that: the skin rash on hands, feet, or other areas becomes easier to identify

    This sequence matters because families often believe the illness begins when the rash appears. Clinically, it usually started earlier.

    If the rash arrives after a day or two of fever and mouth discomfort, that doesn't mean the diagnosis changed. It often means the pattern became easier to recognize.

    Why exposure dating is approximate

    Parents sometimes ask whether the rash can tell you the exact exposure day. Not exactly. But the order of symptoms can still help narrow the likely window. If a child now has clear oral lesions and hand rash, the relevant exposure often sits several days back, not yesterday.

    That's useful for tracing daycare attendance, sibling sleepovers, shared cups, and diapering contacts at home.

    When a Person Is Most Contagious

    The question families usually ask next is not about incubation. It's about spread. When is a child with hand, foot, and mouth disease most likely to pass it on?

    Canadian public health guidance for enterovirus 71-related HFMD says cases are most infectious during the first week of acute illness, may continue shedding virus in stool for weeks, and have an incubation period of 3 to 5 days in Canada's public health information sheet. Operationally, that means the highest-risk window is early illness, even though hygiene still matters after recovery.

    Infographic showing the incubation period and contagion window for hand, foot, and mouth disease.

    The first week matters most

    This is the period when children are usually symptomatic, touching their mouths, drooling, resisting handwashing, and needing close care. In homes and classrooms, that's when saliva, respiratory secretions, blister fluid, and contaminated hands have the most practical relevance.

    The part that confuses parents is stool shedding. A child may feel better and return to normal energy, while viral shedding in stool continues beyond the visibly sick period.

    What to do with that information

    That doesn't mean a child remains equally contagious in all ways for the entire shedding period. It means diapering and toileting hygiene stay important well after fever ends.

    Helpful habits include:

    • Handwashing after bathroom trips or diaper changes
    • Cleaning high-touch surfaces that pick up saliva or dirty hands
    • Keeping separate cups, utensils, and towels during active illness
    • Maintaining routines that reduce mix-ups, like name labels and personal bins. Some families and childcare programs also like practical tips for sick season with kids that make those routines easier to manage.

    For a fuller discussion of return timing and spread after symptoms improve, VirusFAQ also has a related article on how long hand, foot, and mouth is contagious.

    Does presymptomatic spread happen

    The safest way to explain this is careful, not absolute. Because the infectious window overlaps with the end of incubation, spread can occur before the diagnosis is obvious. That's one reason classroom outbreaks seem to “jump” before the first child is formally identified.

    Practical Guidance for Daycare and Home

    Parents and daycare staff don't need a perfect epidemiology model. They need decisions they can make today. The incubation period for hand foot and mouth is most useful when it changes what you do during the days right after exposure and the days right after symptoms begin.

    An infographic titled Practical Guidance for Daycare and Home, outlining six hygiene and safety measures for children.

    Daycare exclusion and return

    A practical exclusion approach is symptom-based, with close attention to the usual timing after exposure.

    • After known exposure: watch closely over the following week for fever, mouth pain, reduced appetite, drooling, or rash.
    • Once illness begins: keep the child home while fever is active and while mouth sores or open blisters make drooling, discomfort, or hygiene difficult.
    • Return when the child can participate safely: a common operational standard is that fever has resolved for at least 24 hours without fever-reducing medicine, and mouth sores or open blisters have healed or crusted enough for routine care.

    That last point is about function as much as infection control. A child who can't drink, can't tolerate normal care, or has weeping lesions still needs home care even if the calendar says several days have passed.

    Cleaning and household routines

    The short incubation window tells you when to be alert. The longer stool-shedding tail tells you what to keep doing after everyone seems better.

    Focus on the places and objects children touch:

    • Toys that go in mouths: clean them promptly and remove shared mouthed toys from circulation during active illness.
    • High-touch surfaces: wipe tables, doorknobs, faucet handles, potty seats, and changing areas regularly.
    • Feeding items: don't share cups, forks, spoons, water bottles, or towels among siblings.
    • Diapering supplies: wash hands carefully after every diaper change, even after symptoms fade.

    For childcare providers reviewing broader sanitation routines, Superstar Nannies childcare safety offers a practical overview that fits well with everyday infection-control habits.

    Parent checklist: Mark the likely exposure date, watch the next week closely, isolate symptoms early, and keep hygiene strict around saliva and stool even after energy returns.

    When to notify others

    Tell daycare, close contacts, or household caregivers as soon as HFMD is suspected, not only after the rash is dramatic. Early notice helps others monitor children during the most relevant part of the exposure window.

    That matters most when the exposed group includes:

    • Very young infants
    • Children who need help with all toileting
    • Immunocompromised contacts
    • Settings with lots of hand-to-mouth behavior

    When to seek medical review

    Most cases are managed at home, but some situations deserve closer attention. Seek medical advice if a child isn't drinking, has signs of dehydration, seems unusually lethargic, or if the diagnosis is uncertain and another rash illness is possible.

    You should also get medical guidance sooner for very young infants, medically fragile children, or settings where several linked cases are appearing and exclusion decisions are becoming complicated.

    The main public-health lesson is simple. Don't think of HFMD as a disease with one magic number. Think of it as a short, fast-moving exposure clock with a dense middle and a thinner tail. That model gives parents, daycare directors, school nurses, and clinicians a better way to decide when to watch, when to isolate, and when to relax.


    Hand, foot, and mouth disease moves quickly, but families can respond calmly when they know what the clock looks like. If you're managing an exposure at home or in childcare, good handwashing, prompt surface cleaning, and ready-to-use disinfecting wipes can make the daily routine much easier.